5 Ways Nixing The Affordable Care Act Could Upend The Entire U.S. Health System

Philadelphia demonstrators protested earlier moves by Republicans to repeal the Affordable Care Act last February. If the ACA is indeed axed as unconstitutional, health policy analysts say, millions of people could lose health coverage, and many aspects of Medicare and Medicaid would change dramatically.
NurPhoto/via Getty Images
hide caption
toggle caption
NurPhoto/via Getty Images
https://www.npr.org/sections/health-shots/2011/08/23/139892320/medicare-trying-bundled-payments-to-save-money-improve-careIf last Friday’s district court ruling that the Affordable Care Act is unconstitutional were to be upheld, far more than the law’s most high-profile provisions would be at stake.
In fact, canceling the law in full — as Judge Reed O’Connor in Fort Worth, Texas, ordered in his 55-page decision — could thrust the entire health care system into chaos.
“To erase a law that is so interwoven into the health care system blows up every part of it,” says Sara Rosenbaum, a health law professor at the George Washington University School of Public Health. “In law they have names for these — they are called super statutes,” she says. “And [the ACA] is a super statute. It has changed everything about how we get health care.”
O’Connor’s decision is a long way from implementation. He still must rule on several other aspects of the suit brought by 18 Republican attorneys general and two GOP governors. And a group of state Democratic attorneys general has promised to appeal O’Connor’s decision, which would send it to the 5th Circuit Court of Appeals and, possibly, the U.S. Supreme Court. The high court has rejected two previous efforts, in 2012 and 2015, to find the law unconstitutional.
Meanwhile, here are five ways that eliminating the ACA could upend health care for many, if not most, Americans:
Millions could lose coverage directly
More than 20 million Americans who previously were uninsured gained coverage from 2010 to 2017. Some of that was due to an improving economy, but many also gained the ability to buy their own coverage, thanks to the law’s federal subsidies to defray the cost of insurance. Other provisions of the Affordable Care Act played a significant role, including its ban on restrictions for people with preexisting medical conditions, expansion of the Medicaid program to more low-income adults and allowing adult children to stay on their parents’ health plans until reaching age 26.
If the law were reversed, federal funding for Medicaid and individual insurance subsidies would stop, and insurers could once again refuse coverage to or charge more for people who have health problems.
Fundamental changes to the health care system could be stymied
The impact of eliminating the ACA could be felt well beyond those people who are the direct beneficiaries of the law.
Gail Wilensky, who ran the Medicare and Medicaid programs under President George H.W. Bush, says such a change “would be very disruptive because so much [of the ACA] has affected the way health care is organized and delivered, and the way insurance is provided.”
For example, says Rosenbaum, the increase in health coverage meant that “suddenly it became possible for health care systems to care for, by and large, an insured population.”
Previously many hospitals, doctors and other health providers spent considerable time and effort figuring out how to treat — without going broke —people who lack insurance.
After the ACA kicked in, these providers began to worry less about whether they would get paid. And the federal government started pushing them to create new initiatives aimed at improving the quality of care.
Those include, for example, measures that base some federal payments on patients’ health outcomes rather than on each individual procedure performed. Under the ACA, the government also encouraged strategies that improve health across the U.S. — like improving the availability of healthful food, bicycle paths and preventive care.
If millions of people lost insurance, Rosenbaum says, those health providers “would have to go back to wondering how they will be able to pay their bills.”
Medicare and Medicaid would be dramatically altered
The popular Medicare program — which covers an estimated 60 million seniors and people with disabilities — was a major focus of the ACA.
Elimination of the federal health law would take away some popular benefits the ACA conferred — everything from free preventive care to the closing of the “doughnut hole” in Medicare’s prescription drug coverage. The doughnut hole refers to a coverage gap that had previously exposed large numbers of beneficiaries to thousands of dollars in drug costs.
The law also changed the way Medicare paid for hospital, home health and outpatient care. Many current payment policies are based on authority provided by the ACA, and if it went away, Medicare would have to rewrite those payment regulations. Millions of beneficiaries belong to accountable care organizations that were created under the health law, and it is unclear how their care would be affected.
The biggest change in the Medicaid program would be the elimination of the expansion of coverage. Loss of the ACA would also roll back a 23-percentage-point boost in Medicaid prescription drug rebates, which has saved states billions of dollars, according to Cindy Mann. She ran Medicaid under President Barack Obama and is now a partner at the health consulting firm Manatt Health.
The ACA required states to calculate Medicaid eligibility differently — changing what counts as income — so all the work states did to alter their information systems would have to be recalculated, she says.
Wide array of health programs at risk
Shorthand descriptions of the health law often stop at its provisions providing consumer protections and expanding Medicaid. But the ACA included sweeping changes to other parts of the health system that rarely get mentioned.
For example, it created the first pathway for Food and Drug Administration approval of generic copies of expensive biologic drugs, by incorporating the Biologics Price Competition and Innovation Act of 2009. Biologic drugs are more difficult to reproduce than other types of medications.
Also hitching a ride on the ACA was a long-delayed bill providing permanent spending authority for programs provided by the Indian Health Service, which serves Native Americans.
And the law included a series of grant programs to help train more health professionals who would be needed to treat the millions of newly insured Americans.
All those programs would be thrust into doubt by invalidating the law.
Loss of the ACA also would impact a popular program that predates Obamacare: the Health Insurance Portability and Accountability Act, or HIPAA.
The ACA’s protections for preexisting conditions — banning insurers from charging people with health problems higher premiums or refusing to sell to them altogether — built on similar protections for people with employer insurance. Congress included those protections in HIPAA, which was enacted in 1996. And far more people are touched by HIPAA than by the ACA, because far more people get health insurance through their employer than the individual market.
However, when Congress wrote the ACA, it incorporated HIPAA safeguards into the preexisting condition provision. That means if the ACA is struck down, the HIPAA protections might disappear as well.
Even the Trump administration’s health agenda could be compromised
President Donald Trump has railed against the health law, but his Department of Health and Human Services has a priority list that relies in some significant ways on the continued existence of the ACA.
For example, efforts to address the opioid epidemic — one of the administration’s top health challenges — could be seriously set back if the Medicaid expansion were to end. Medicaid is the largest single payer for mental health and substance abuse treatments.
Much of the president’s effort to limit drug prices flows through the Center for Medicare & Medicaid Innovation (CMMI), which was created by the ACA and would lose its legal authority if the law became invalid.
Similarly, the administration is using this center to pursue “bundling” payments for certain surgical procedures — an effort to try to get more value for dollars spent.
Kaiser Health News, a nonprofit news service, is an editorially independent program of the Kaiser Family Foundation and not affiliated with Kaiser Permanente. KHN senior correspondent Phil Galewitz contributed to this story.
'Realization Of An Impossible Dream': MLB And Cuba Make Historic Deal

Los Angeles Dodgers’ Yasiel Puig in October. On Wednesday, U.S. Major League Baseball and Cuba’s baseball federation reached an agreement, allowing Cuban players to sign with U.S. teams without defecting.
Jae C. Hong/AP
hide caption
toggle caption
Jae C. Hong/AP
A new inning has begun for Cuban baseball players, after a historic agreement will allow the athletes to sign with U.S. teams without needing to defect.
Major League Baseball and the Major League Baseball Players Association announced Wednesday that they reached an agreement with the Cuban Baseball Federation after years of negotiating.
Under the deal, Cuba must release baseball players who are at least 25 or with more than six years of experience, and any major league club with whom they sign will pay Cuba’s baseball federation a “release fee.” The athlete will be able sign with a club while in Cuba, apply to the U.S. for a work visa and return to their homeland during the off-season.
The agreement is meant to stem the trafficking of Cuban athletes, its architects say. Since the U.S. embargo against Cuba started in 1962, baseball players on the island have had no choice but to defect and establish residence in a third country before signing a contract with a major league club in the United States.
That has led to a slew of perilous and harrowing encounters, including trafficking and extortion. Los Angeles Dodgers’ right fielder Yasiel Puig was smuggled out of Cuba to Mexico, then held by gangsters for ransom before receiving a $42 million contract.
“Establishing a safe, legal process for entry to our system is the most important step we can take to ending the exploitation and endangerment of Cuban players who pursue careers in Major League Baseball,” MLB Players Association Executive Director Tony Clark said in a statement. “The safety and wellbeing of these young men remains our primary concern.”
Deputy Commissioner Dan Halem told Reuters that the payments to Cuba are acceptable despite the sanctions because the Cuban Baseball Federation isn’t part of the island’s government.
A State Department official told NPR in an emailed statement that the agency is aware of the agreement and that baseball players will still have to go to another country to apply for a work visa, in accordance with U.S. policy.
If athletes choose to defect, they will face a mandatory waiting period before being eligible to sign.
It is unclear when the agreement will take effect. MLB did not immediately respond to NPR’s request for comment.
Similar agreements exist with Korea, Taiwan and Japan.
As part of their effort to form a deal, Major League Baseball spent more than $1.3 million lobbying on Cuban issues last year and nearly $1 million through the third quarter of 2018, Yahoo reported.
Baseball agent and consultant Joe Kehoskie told The Washington Post that despite an end to their legal obstacles, players will “likely end up worse off financially.” A reported 15 to 25 percent release fee to Cuba’s baseball federation is “roughly the same percentage Cuban players are currently paying to smugglers, and they’d likely be signing less-valuable contracts, since they’d be negotiating within a more restrictive [release] system, or draft, rather than as free agents.”
Emily Mendrala, executive director of the Center for Democracy in the Americas, called it “great news for Cuba, for the U.S., for the safety of Cuban baseball players and their families, and for baseball fans everywhere.”
In a statement, she described the long, shared history of baseball between the U.S. and Cuba, from Jackie Robinson training in 1940s Havana to a 2016 game between Cuba’s national team and Florida’s Tampa Bay Rays, with then-Presidents Barack Obama and Raul Castro in attendance.
Despite economic isolation, Cuba has continued to produce renowned baseball players over the years, including Puig, the Boston Red Sox’s Rusney Castillo, Chicago White Sox’s Jose Abreu, and former pitcher Orlando Hernandez.
“Knowing that the next generation of Cuban baseball players will not endure the unimaginable fate of past Cuban players is the realization of an impossible dream for all of us,” Abreu said in a statement. “Dealing with the exploitation of smugglers and unscrupulous agencies will finally come to an end for the Cuban baseball player.”
5-Time Gold Medalist Missy Franklin Retires From Swimming

Swimming champion Missy Franklin announced her retirement from the sport in an emotional letter to ESPN.com on Wednesday. She is 23.
Simon Hofmann/Getty Images for Laureus
hide caption
toggle caption
Simon Hofmann/Getty Images for Laureus
Five-time Olympic gold medalist and world record-holder Missy Franklin announced her retirement from swimming in an impassioned letter to ESPN.com on Wednesday, citing chronic shoulder pain that has ravaged her body and psyche over the last years of her career.
“It took me a long time to say the words, ‘I am retiring.’ A long, long time. But now I’m ready,” she said.
“I’m ready to not be in pain every day. I’m ready to become a wife and, one day, a mother. I’m ready to continue growing each and every day to be the best person and role model I can be. I’m ready for the rest of my life,” Franklin wrote.
The 23-year-old became an Olympic sensation during the 2012 London games where she was hailed by authorities in the sport as the new, best hope of American swimming. And she did not disappoint.
At 17, with her braces recently removed, she beamed from the podium time and time again, earning a total of five medals and becoming the first woman to win four gold medals in a single Olympics in any sport.
Franklin broke the world record for the 200-meter backstroke with a record time of 2:04:06, which netted the teen athlete a third gold medal at the games. At the time the young phenom was still training with her childhood swimming coach.
Over her amateur and professional career the swimming champion has won more than two dozen medals and accolades, including FINA World Swimmer of the Year in 2011 and 2012. But things began to unravel leading into Franklin’s second Olympic games.
“I’ve been very open about what I went through as I prepared for the Olympics in 2016 and talked openly about the struggles I endured, which included shoulder pain whenever I tried to train or compete, depression, anxiety and insomnia. It was also the year when I began to fully accept the fact that something was wrong with my body and it wasn’t working the way it was supposed to work,” Franklin said in the letter.
While she qualified for the games in Brazil she did not make it to the finals in either of her strongest events — the 200-meter freestyle and the 200-meter backstroke. Her only medal was a gold in the 4×200-meter freestyle relay.
Franklin described years of “the worst” shoulder pain, surgeries, physical therapy and mental anguish. She explained she has been diagnosed with “severe chronic tendonitis of both the rotator cuff and the bicep tendon.”
She said she has gone through three rounds of cortisone shots, including one just before the U.S. nationals in July in which she finished third in the C final of the 200-meter freestyle.
And just as she prepared to begin her “comeback, to prove everyone wrong, to show what a fighter” she is, Franklin was told she would need to have another surgery. She decided she couldn’t go through with it.
“I’ve been in too much pain, for too long, to go through another surgery with a longer recovery time and no guarantee it would even help,” she said.
Looking toward the future, Franklin said her “greatest dream in life, more so than Olympic gold, has always been becoming a mom.”
“This is by no means the end,” she added. “Rather, I choose to look at this as a new beginning. Swimming has been, and always will be, a big part of my life and I absolutely plan to stay involved in what I feel is the best sport in the world, just in a different way.”
Judge Who Invalidated Obamacare Has Been A 'Go-To Judge' For Republicans, Critics Say

In 2015, demonstrators in Washington, D.C. urged Supreme Court justices to save the Affordable Care Act from a legal challenge. The federal health law survived, but now faces a new challenge, from a controversial ruling last week by U.S. District Judge Reed O’Connor; he says the ACA is invalid. An appeal of his decision is underway.
Bloomberg/Bloomberg/Getty Images
hide caption
toggle caption
Bloomberg/Bloomberg/Getty Images
U.S. District Judge Reed O’Connor has a history of siding with Republicans on ideologically motivated lawsuits. The ruling last week, in which he sided with the GOP on a challenge to the Affordable Care Act, was not a one-off.
Critics say, in fact, his history is ultimately why that case was before him in the first place.
By all accounts, O’Connor’s ruling is sweeping. It says the entire health care law became invalid when Congress zeroed out, in 2017, the tax penalty for Americans who don’t have health insurance — a penalty that had been tied to what’s known as the law’s individual mandate that nearly everyone have insurance.
“I think he went too far in rejecting the entire law,” says Josh Blackman, a conservative legal scholar and professor at the South Texas College of Law in Houston. “I think he could have stopped short and simply severed the Obamacare mandate.”
While O’Connor’s decision may seem a bit extreme to some legal scholars, it wasn’t surprising.
Justin Nelson, a law professor at the University of Texas at Austin, says if you know anything about O’Connor’s past rulings, this was predictable.
“In case after case,” Nelson says, “what he has shown is that the has tended to side with the Republican attorneys general who are bringing ideological suits.”
Nelson recently ran an unsuccessful campaign to oust Texas Attorney General Ken Paxton, who led this multistate legal challenge to the health care law. Nelson says Paxton and the other Republican attorneys general have filed lawsuits in the U.S District Court for the Northern District of Texas because they know there’s a good chance they’ll get O’Connor as the judge.
“Judge O’Connor has been the go-to-judge for Ken Paxton and Republican attorneys general who want to file ideological suits in any court across the country,” Nelson says. “Reed O’Connor is their best shot to get a ruling that they like.”
O’Connor, who did not respond to NPR’s requests for comment, was a Republican staffer on Capitol Hill before he was nominated to the federal bench by George W. Bush in 2007. So far, he’s had to weigh-in on at least a couple of contentious issues.
For example, O’Connor is known for striking down an Obama-era rule that protected transgender students. In that case he also sided with Ken Paxton, who filed that legal challenge.
“They’ve done this over and over again on the hope that Judge O’Connor would rule on behalf of an ideological agenda,” Nelson says. “And I don’t think that is proper. I don’t think that is right.”
Paxton has filed lawsuits in other courts, too. He filed challenges to Obama-era immigration laws in a court in South Texas, which also has a reliably conservative judge on the bench.
However, Blackman believes criticism of this practice is “overblown.”
“All lawyers generally file the case where it leads to the best chance of success,” Blackman says. “And to the extent that [there’s a] criticism — that’s criticism of the attorney general and not of the judge. The judge doesn’t control which cases come to him.”
Furthermore, because O’Connor is getting a lot of ideological lawsuits brought to him, it’s making his voting record more controversial, Blackman adds.
“I think by virtue of the attorney general’s form selection,” he says, “Judge O’Connor’s had a greater share than average of hot button issues.”
However, Blackman says he is concerned that criticisms of controversial opinions are increasingly shifting toward the judges who issue the opinions – instead of toward the decisions themselves.
“President Trump does this all the time,” Blackman says.”Politicians do it all time. And usually this happens to Supreme Court justices, but here it is being done to a district court judge in Fort Worth — who, 99 percent of his docket no one will even know about.”
No matter how controversial O’Connor’s ruling on the health care law, Blackman says, the decision over the Affordable Care Act will now pass to another judge, as the case moves on to a higher court.
Why The U.S. Remains The Most Expensive Market For 'Biologic' Drugs In The World

Susie Christoff tried several drugs to cope with her painful psoriatic arthritis before finding Cosentyx worked the best. The problem was the cost.
Chris Bartlett/for Kaiser Health News
hide caption
toggle caption
Chris Bartlett/for Kaiser Health News
Europeans have found the secret to making some of the world’s costliest medicines much more affordable, as much as 80 percent cheaper than in the U.S.
Governments in Europe have compelled drugmakers to bend on prices and have thrown open the market for so-called biosimilars, which are cheaper copies of biologic drugs often derived from living organisms.
The brand-name products — ranging from Humira for rheumatoid arthritis to Avastin for cancer — are high-priced drugs that account for 40 percent of U.S. pharmaceutical sales.
European patients can choose from dozens of biosimilars — 50 in all — which have stoked competition and driven prices lower. Europe approved the growth hormone Omnitrope as its first biosimilar in 2006, but the U.S. didn’t follow suit until 2015 with cancer-treatment drug Zarxio.
The U.S. government generally stops short of negotiating prices and drugmakers with brand-name biologics have used a variety of strategies — from special contracting deals to overlapping patents known as “patent thickets”— to block copycat versions of their drugs from entering the U.S. or gaining market share.
As a result, only six biosimilars are available for U.S. consumers.
European countries don’t generally allow price increases after a drug launches and, in some cases, the national health authority requires patients to switch to less expensive biosimilars once the copycat product is proven safe and effective, says Michael Kleinrock, research director for IQVIA Institute for Human Data Science.
If Susie Christoff, a 59-year-old who suffers from debilitating psoriatic arthritis, lived in Italy, the cost of her preferred medicine would be less than quarter of what it is in the U.S., according to data gathered by GlobalData, a research firm.
Christoff tried a series of expensive biologics before discovering a once-a-month injection of Cosentyx, manufactured by Swiss drugmaker Novartis, worked the best.
Without the medicine, Christoff says her fingers can swell to the size of sausages.
“It’s 24/7 constant pain in, like, the ankles and feet,” says Christoff, who lives in Fairfax, Va. “I can’t sleep, [and] I can’t sit still. I cry. I throw pillows. It’s just … awful.”
At first, Christoff’s copay for Cosentyx was just $50 a month. But when a disability led her to switch to a Medicare Advantage plan, her out-of-pocket costs ballooned to nearly $1,300 a month — more than three times her monthly car loan.
Christoff, with the help of her rheumatologist, Dr. Angus Worthing, tried Enbrel, Humira and other drugs before finding Cosentyx, the only drug that provides relief.
Christoff’s case is “heartbreaking,” Worthing says.
Novartis declined to respond to questions about Cosentyx’s price. Instead, like other pharmaceutical companies, Novartis says it offers patient assistance programs for those who can’t afford the drug. Christoff says she doesn’t qualify for financial assistance.
Like other biologics, Cosentyx costs thousands of dollars per month. The annual cost of Christoff’s treatment runs about $65,000 in the U.S. In Italy, where competition and price negotiations play a bigger role, it would run about $15,000, according to GlobalData.
In England, Dr. Christopher Griffiths, a lead researcher at the National Institute for Health Research who treats patients with Cosentyx, says the National Health Service would pay about 10,000 pounds, or less than $13,000.
And those drastic price differences are true even though there is no biosimilar version of Cosentyx yet available in Europe, and might not be for years.
The cost of the drug is taking a toll on Christoff.
This past summer, her progressive disease made it difficult to enjoy the annual family vacation with her three grown children and their kids in Virginia Beach, Va. “I can’t get down on the sand to play with my kids without help. I can’t get up without help,” Christoff recalled. “I’m not ready to stop trying. But I’m also not ready to go through my entire retirement fund to walk.”
Unlike Cosentyx, rival drugs — Humira, Enbrel and Remicade — all face biosimilar competition in Europe. Only Remicade has competition from a lower-cost biosimilar in the U.S., and Humira isn’t expected to have a copycat competitor in the U.S. market until 2023. Humira, made by AbbVie, is the world’s top-selling drug.
In late October, Wall Street analyst Ronny Gal at Sanford C. Bernstein & Co. noted that AbbVie agreed to drop Humira’s price by 80 percent in one Nordic country to combat biosimilar competition.
During the company’s quarterly conference call in November, AbbVie chief executive Richard Gonzalez says the drug’s discount was as low as 10 percent and as high as 80 percent across the continent, with the highest discounts in Nordic countries.
“These are markets where it’s winner takes all across the entire … category, so includes Remicade and Enbrel as well,” Gonzalez said, adding that Nordic countries represent about 4-5 percent of overall revenue in AbbVie’s international business.
Concerned about how much biologics cost the U.S. health system and patients, Food and Drug Administration Commissioner Scott Gottlieb announced an “action plan” this summer that included tapping the Federal Trade Commission for help, saying he was “worried” about the biosimilar market.
“The branded drug industry didn’t build its success by being business naive; they are smart competitors,” Gottlieb told an audience full of advocates, industry insiders and researchers at the Washington, D.C.-based Brookings Institution in July. “But that doesn’t mean we need to embrace all of these business tactics or agree with them and think they are appropriate.”
One of these business tactics involves so-called rebate traps, in which financial deals are cut to make sure patients can get only a biologic, not a biosimilar. International drugmaker Pfizer alleged in a September 2017 lawsuit that exclusionary contracts created by Johnson & Johnson prevented use of its biosimilar by health insurers, hospitals and clinics.
Johnson & Johnson’s wildly successful biologic Remicade, the brand-name version of infliximab, produced $6.3 billion in worldwide revenue in 2017. Pfizer launched its copycat drug, Inflectra, in the U.S. in October 2016, noting in the announcement that it would price the drug at a 15 percent discount to Remicade’s wholesale price.
Still, health systems such as Geisinger Health, based in Pennsylvania, say they have had difficulty switching to the less expensive alternative. “J&J has done a really good job of entrenching themselves in the market,” says Jason Howay, manager of formulary services at Geisinger.
The health system ultimately decided it wanted to switch all adults to Pfizer’s biosimilar, saying it provided the same quality of treatment. But Johnson & Johnson had “bundled” the prices of other drugs with Remicade. So if Geisinger stopped using Remicade on adult patients, J&J could stop providing discounts on other drugs, such as those used for cardiology, Howay explained. “It weaves a very tangled web.”
A spokeswoman for Janssen, Johnson & Johnson’s main pharmaceutical subsidiary, says the drugmaker does offer “more attractive contract terms” to buyers who use a wider range of J&J medicines. “Our contracting approach has always prioritized access for patients and their providers,” Meredith Sharp says.
Geisinger negotiated with biosimilar maker Pfizer and won still lower prices to make up for lost savings on the other J&J drugs. It’s now transitioning all adult patients to the less expensive biosimilar.
Another business tactic is creating patent thickets, in which drugmakers win numerous patents to block competitors entirely. Humira, which treats arthritis and Crohn’s disease, has more than 100 patents protecting it in the U.S. By contrast, cheaper biosimilar versions of the AbbVie drug rolled out in October in Europe, where patent laws are less likely to offer such protection.
Such tactics are stifling competitors, according to Bruce Leicher, a former senior vice president and general counsel for Momenta Pharmaceuticals, a Cambridge, Mass., biotechnology company focused on rare-disease drug development. Smaller companies are “struggling now” to plan launches of new drugs. Momenta cut half its staff in October, including Leicher, and announced plans to shift away from five biosimilar development programs.
Leicher says the FDA’s biosimilar action plan under Gottlieb is a good first step but “would have been wonderful to see five years ago.”
Other lingering regulatory burdens have hampered biosimilar adoption as well. This summer, Medicare began reimbursing doctors and hospitals differently for biosimilars. Before that change, patients could pay more out-of-pocket for less expensive rheumatoid arthritis biosimilars than for the brand-name biologics.
And, unlike more chemical compound generics, like aspirin, a pharmacist cannot automatically replace a brand-name biologic with the biosimilar. More than 40 states have passed laws around how and when doctors and pharmacists can substitute a biosimilar for a biologic. Federal guidelines are still not established.
In addition, the FDA requires each biosimilar name to include a random suffix, ostensibly to differentiate it from the biologic drug. That can be confusing and could cause patients and physicians to believe the products are significantly different in quality, says Christine Simmon, who promotes biosimilars for the trade group Association for Accessible Medicines.
She says the naming convention “fuels the fire” of a broader debate about whether to trust biosimilars, adding, “Making sure doctors and patients are comfortable with the products is integral to uptake.”
Kaiser Health News is a nonprofit news service covering health issues. It is an editorially independent program of the Kaiser Family Foundation that is not affiliated with Kaiser Permanente.
Why Aren't More Users Of Opioids Or Meth Screened For Hepatitis C?

The initial test for hepatitis C is an inexpensive blood test to check for antibodies that indicate the person’s been exposed to the virus. If that antibody test is positive, a second test is done to see if the virus is circulating in the bloodstream — a sign there’s an infection that needs treatment.
BSIP/UIG/Getty Images
hide caption
toggle caption
BSIP/UIG/Getty Images
When people seek help at a drug treatment center for an opioid addiction, concerns about having contracted hepatitis C are generally low on their list.
They’ve often reached a crisis point in their lives, says Marie Sutton, the CEO of Imagine Hope, a consulting group that provides staff training and technical assistance to facilitate testing for the liver-damaging virus at more than 30 drug treatment centers in Georgia.
“They just want to handle [their drug problem],” Sutton says. “Sometimes they don’t have the bandwidth to take on too many other things.”
And although health care facilities that serve people who use drugs are well-positioned to initiate screening, studies show that often doesn’t happen.
It’s an enormous missed opportunity, say public health specialists.
“It’s a disease that can be cured the moment we identify somebody,” says Tom Nealon, president and CEO of the American Liver Foundation. “Not testing is incomprehensible when you look at what hepatitis C does to their bodies and their livers.”
As the number of people who inject drugs has soared, the rate of infection with hepatitis C — which is frequently tied to sharing needles — has climbed steeply, too.
People with a hepatitis C infection can go for years without symptoms, so may have no inkling they’re sick. That delayed onset makes screening important, say health researchers, since infected people may unwittingly infect others.
Still, while screening people who misuse drugs can break the cycle of transmission, public health advocates say a number of obstacles — a lack of money, staff or other resources — may keep substance abuse facilities from going that route.
“Reimbursement rates for hepatitis C testing often don’t match the cost,” says Andrew Reynolds, hepatitis C and harm reduction manager at Project Inform, a advocacy group for patients. If people test positive, they need to be linked to treatment, and financial support for staffing to do that is often limited, he says.
Only 27.5 percent of 12,166 substance abuse facilities reported offering testing for hepatitis C in 2017, according to research published on the blog for the journal Health Affairs in October. It was one of the first studies to look at this issue since the federal government began reporting on testing for HIV and hepatitis C in its national survey of substance abuse and treatment services in 2016.
When researchers narrowed their analysis to the much smaller number of opioid treatment programs that are federally certified to use methadone and other drugs in treatment, a higher, but still not overwhelming, proportion — just over 63 percent — said they offered screening for hepatitis C.
“We certainly thought the numbers would be higher,” says Asal Sayas, a co-author of the analysis and director of government affairs at amfAR, the Foundation for AIDS Research. “Testing is one of the most fundamental forms of prevention.”
In primary care settings, the situation sometimes isn’t much better, even when patients have a diagnosed “opioid-use disorder.”
An analysis by Boston Medical Center researchers of nearly 270,000 medical records of people aged 13 to 21 who visited federally qualified health centers from 2012 to 2017 found that only 36 percent of the 875 patients with that diagnosis were tested for hepatitis C.
“Even in a setting with an identified risk factor in opioid-use disorder, too few youths are being screened for hepatitis C,” says Dr. Rachel Epstein, a postdoctoral research fellow in infectious diseases at Boston Medical Center and a co-author of the study.
Hepatitis C is a virus that causes inflammation of the liver, in some cases leading to scarring, liver cancer and death. It is transmitted through blood, including contaminated needles that people share when they inject drugs.
The initial test for hepatitis C is an inexpensive blood test to check for antibodies that indicate the person’s been exposed to the virus. If that antibody test is positive, a second test is necessary to find out if the virus is circulating in the bloodstream — that would be a sign of an infection that needs treatment. The second test can cost several hundred dollars, experts say.
To be sure, some federally qualified health centers have made testing for hepatitis C a priority. Clinicians at two community health centers run by Phildadelphia Fight — which was established as an AIDS service organization — test many of their patients who are at high risk of having a hepatitis C infection because of their injection-drug use or unsafe sexual practices, such as having sex with an infected partner. Medical personnel get a reminder in the patient’s electronic medical record to do the screenings, often on an annual basis.
“That’s something pretty basic that we’ve done in our community health centers to make sure we’re testing people and providing a cure,” says Dr. Stacey Trooskin, director of viral hepatitis programs at the FIGHT centers and clinical assistant professor at the University of Pennsylvania Perelman School of Medicine.
Among at least 3.5 million people who have the disease, most are baby boomers who were infected before routine screening of donated blood began in the early 1990s. In recent years, as the opioid epidemic has taken hold, new infections have been concentrated among young people who inject drugs — in particular those between ages 18 and 29, according to the federal Centers for Disease Control and Prevention.
Complicating the effort to get people screened is the fact that many of the people who enroll in drug treatment programs are uninsured, says Imagine Hope’s Sutton. In states that have expanded Medicaid under the Affordable Care Act, the program generally picks up the tab for hepatitis C testing and treatment, though often with restrictions.
But 14 states, including Georgia, haven’t expanded that coverage for adults who have incomes up to 138 percent of the federal poverty level ($16,753 for one person).
Insurance coverage isn’t the only challenge. If people have to come back to a clinic for the second test, chances are they may fall through the cracks, and not get that follow-up.
When a patient tests positive, a nurse or counselor at the drug treatment center — who is likely already overtaxed, just working with patients to address their addiction — must also carve out time to explain this new diagnosis and talk through treatment options.
“There’s a whole system of care that needs to be built for these people,” Sutton says, “and, unlike [for] HIV, it doesn’t exist for hepatitis C at this time.”
As with many other clinics around the country, hepatitis C testing at Georgia drug treatment centers is supported with funding from the Focus program, sponsored by drugmaker Gilead; it was the first company to offer a new class of highly effective drugs that generally cure hepatitis C in three months or less with few side effects.
Finding resources to pay for treatment is also difficult. The high costs of the new drugs when they were introduced led some public and private insurers to strictly limit access. But, in recent years, drug prices have come down as more drugs hit the market and many states have loosened Medicaid restrictions.
For example, New Mexico’s Medicaid program doesn’t require that people be sick or abstain from using illicit drugs or alcohol for a time before starting treatment.
Still, “hepatitis C testing remains out of reach for many because their providers aren’t aware that their patients can get treated,” says Kimberly Page, an epidemiologist and professor of internal medicine at the University of New Mexico, who focuses her study on hepatitis C.
Kaiser Health News, a nonprofit news service, is an editorially independent program of the Kaiser Family Foundation and not affiliated with Kaiser Permanente.
Bill Of The Month: $43,208 For Repeat Surgery To Replace Broken Medical Device

Sarah Witter fractured two bones in her lower left leg while skiing in Vermont last February. She had two operations to repair the damage. The second surgery was needed to replace a metal plate that broke after it was implanted.
Matt Baldelli for KHN
hide caption
toggle caption
Matt Baldelli for KHN
Sarah Witter couldn’t catch a break even though her leg had gotten several.
As she lay on a ski trail in Vermont last February, Witter, now 63, knew she hadn’t suffered a regular fall because she couldn’t get up. An X-ray showed she had fractured two bones in her lower left leg.
A surgeon at Rutland Regional Medical Center screwed two gleaming metal plates onto the bones to stabilize them. “I was very pleased with how things came together,” the doctor wrote in his operation notes.
But as spring ended, the wound started to hurt more. In June, Witter returned to the doctor. “He X-rayed it and said it broke,” she said. “And I was thinking, what broke? And he said, the plate. He said they do sometimes.”
The doctor performed another operation, removing the cracked plate and replacing it with a larger one.
Witter said she had been dutifully following all the instructions for her recovery, including going to physical therapy and keeping weight off her leg.
“I was, of course, thinking, ‘What did I do?’ ” Witter said. “The doctor said right off the bat it was nothing I did.”
Then the bill came.
Patient: Sarah Witter, a retired teacher and ski buff who had moved from Pennsylvania to Vermont for the outdoorsy lifestyle.
Total bill: $99,159 for emergency services, therapy and hospital care, including $52,587 for the first surgery and $43,208 for the second surgery. Altogether, Witter’s insurer, Aetna, paid $76,783. Witter paid $18,442 — including $7,808 for the second surgery. About half of Witter’s total expenses were copayments; another $7,410 was the portion of hospital charges that Aetna considered unreasonably high and refused to pay.
Service provider: Rutland Regional Medical Center, the largest community hospital in Vermont, performed the surgeries. Emergency services, anesthesia and physical therapy were done by other providers.
Medical service: In February, two metal plates called bone fixation devices and manufactured by Johnson & Johnson’s DePuy Synthes division were surgically attached to two lower leg bones Witter had fractured in a skiing accident. These plates are long, narrow pieces of metal with holes drilled in them at regular intervals for screws to attach them to the bones. A crack had developed in one of the plates running from the side of one of those holes to the edge of the plate. A second surgery was required to remove the plate and replace it.
What gives: When devices or treatments fail and need to be replaced or redone, patients and their insurers are typically expected to foot the bill. That may be understandable if a first course of antibiotics doesn’t clear a bronchitis, requiring a second drug. But it is more problematic — and far more expensive — when a piece of surgical hardware fails, whether it’s a pacemaker, a hip that dislocates in the days after surgery or a fractured metal plate.
Warranties, standard features at an electronic store or a car dealership, are rare for surgeries and in the medical device industry.
Dr. James Rickert, an orthopedic surgeon in Indiana and president of the Society for Patient Centered Orthopedics, said a plate like the one implanted in Witter’s leg can fail if the surgeon doesn’t line it up correctly with the bone, although usually that causes the screws to break or back out. A plate also can fail if the patient puts too much weight on it or doesn’t follow other recovery instructions. There can also be a flaw in the implant.

If implanted medical devices fail, as one of Witter’s metal plates did, patients and their insurers usually have to pay for repairs. “I hate to pay for it again, and the doctor clearly said it wasn’t anything I did,” she said.
Matt Baldelli for KHN
hide caption
toggle caption
Matt Baldelli for KHN
“When the plate breaks, it’s usually from overworking it, or a defect in the plate itself,” Rickert said. “The vast majority of people follow their instructions and are honest about it. If a person comes in and tells you they’ve been following their instructions and the surgery’s done properly, to me that’s a hardware failure.”
Nancy Foster, vice president for quality and patient safety policy at the American Hospital Association, said sometimes hospitals won’t charge for a second surgery “if they were aware that it was something they did that caused the patient to need follow-up care.”
Rutland Regional, Witter’s hospital, wouldn’t discuss Witter’s care or bills, even though she gave it permission to do so. “The organization is not comfortable in getting into the specifics of an individual patient’s case,” a spokeswoman wrote. The hospital also declined to discuss under what circumstances, if any, it would discount a second surgery’s cost because of the first’s failure.
Hospitals don’t consider it their responsibility if a medical device failure is the problem, Foster said. But manufacturers are reluctant to take the blame for an unsuccessful surgery.
AdvaMed, a trade group for medical device manufacturers, said some companies will provide replacement devices if theirs failed, but others don’t, especially if the failure of a procedure cannot “easily be attributed” to the device, the group said in a written statement.
“There are numerous factors outside of a manufacturer’s control — and unrelated to the safety of the device as designed — that could result in a device not performing as intended,” AdvaMed said.
These devices aren’t cheap: Witter’s hospital billed $9,706 for the first set of plates. It billed $12,860 for the replacement and an extra piece of equipment to attach it.
DePuy Synthes, which manufactured Witter’s plates, said in a written response that “in rare circumstances” metal plates “may fracture under normal weight-bearing or load-bearing in the absence of complete bone healing.” Even then, the company said, that is a chance patients have to take.
AdvaMed said it doesn’t keep statistics on device performance, and DePuy didn’t respond to questions about how often its plates fail.
Resolution: The second surgery delayed Witter’s recovery by four months and prevented her from gardening, golfing, hiking, biking and motorcycling through the summer and fall, as she usually does. “I was pretty much chair-bound for 20 weeks,” she said.
In November, she wasn’t able to join her husband and son on a trip to Iceland. Instead of volunteering at a nearby ski resort, as she had done for six years — and which carries the benefit of a free season pass — Witter said she tried selling hand warmers and lip balm out of a small kiosk and watching the skiers through a window. She said she had to quit after six days because of the pain in her feet.
“The biggest annoyance with this whole thing, even though it took eight months out of my life, is I hate to pay for it again, and the doctor clearly said it wasn’t anything I did,” she said.
Aetna said in a statement that while it doesn’t allow providers to charge for indisputably inept medical mistakes such as leaving a surgical sponge in a patient or operating on the wrong limb, a broken plate doesn’t qualify for such protection. (Medicare follows a similar approach.)
After reviewing Witter’s records, Aetna said it concluded the hospital had billed Witter for the portion of charges Aetna had considered excessive —a practice known as “balance billing.” While Aetna cannot reject those charges because the hospital doesn’t have a contract with it, the spokesman said Aetna would try to negotiate with the hospital on Witter’s behalf to reduce the bill.
Rutland Regional, however, indicated in its statement that the only reason it would discount a bill was for people who had inadequate insurance or were suffering financial hardship from the size of the bills. Witter said she doesn’t meet the hospital’s criteria.
The hospital invited her to meet with her surgeon and its chief financial officer.
The takeaway: Witter brought up the seeming unfairness of the double charges to the hospital’s billing department as well as to her doctor, who, she said, was “charming,” but told her “he had no wiggle room to do anything.” Patients are usually out of luck when a second surgery is needed because of the failure of a medical device or a surgeon’s mistake. A few places, most prominently the Geisinger health system in Pennsylvania, offer warranties for hip and knee, spine and coronary artery bypass surgeries, among other procedures.
AdvaMed says that if a company provides a replacement, the hospital or surgeon isn’t supposed to bill Medicare or the patient for the equipment — even if the operation incurs charges.
Patients should scrutinize their bills and question their doctor and hospital or surgical center about charges for replacement devices.
If the doctor or hospital is partially at fault for the failure of the first procedure, request that part or all of the costs of the second surgery be waived. Get it in writing so you can make sure the billing department follows through. Also, in a medical market where insurers want to pay only for value-based care, let your insurer or employer’s human resources department know that you are being charged twice for the same surgery. Let them fight the battle for you.
NPR produced and edited the interview with Kaiser Health News’ Elisabeth Rosenthal for broadcast. Nina Keck, a reporter with member station WVPR in Vermont, provided audio reporting.
Do you have an exorbitant or baffling medical bill that you’d like KHN and NPR to look into? You can tell us about it and submit a copy of the bill here.
KHN is a nonprofit news service covering health issues. It is an editorially independent program of the Kaiser Family Foundation that isn’t affiliated with Kaiser Permanente.
An Epidemic Is Killing Thousands Of Coal Miners. Regulators Could Have Stopped It

Greg Kelly at home in Delphia, Ky. A former coal miner, Kelly has an advanced stage of black lung disease known as complicated black lung or progressive massive fibrosis.
Rich-Joseph Facun for NPR
hide caption
toggle caption
Rich-Joseph Facun for NPR
Greg Kelly’s grandson, Caden, scampers to the tree-shaded creek behind his grandfather’s house to catch crawdads, as Kelly shuffles along, trying to keep up. Kelly’s small day pack holds an oxygen tank with a clear tube clipped to his nose. He has chairs spaced out on the short route so he can stop every few minutes, sit down and catch his breath, until he has enough wind and strength to start out again for the creek.
“I just pray that the Lord give me as much time as I can with him,” Kelly said, his eyes welling with tears. “He just lightens my life. I want to be as fun with him as I can. And do as much as I can with him.”
Caden is 9 years old, and even at his age he knows what happened to his paw-paw at the Harlan County, Ky., coal mines where Kelly labored as a roof bolter for 31 years.
“That coal mine made your lungs dirty, didn’t it?'” Kelly recalled Caden asking. “Yeah it did. … And I can’t breathe and I have to have my backpack to breathe,” Kelly told him.

Former coal miner Danny Smith and his family used to ride their ATVs and go camping on this reclaimed strip mining site in Pike County, Ky. But Smith is no longer able to do such things because of his advanced black lung disease.
Rich-Joseph Facun for NPR
hide caption
toggle caption
Rich-Joseph Facun for NPR
It’s a familiar tale across Appalachia. Two hours north and east, beyond twisting mountain roads, Danny Smith revved up a lawn mower. He wore jeans, a T-shirt and a white face mask stretching from eyes to chin, and he pushed only about 15 feet before he suddenly shut off the mower, bent to his knees and started hacking uncontrollably.
“Oh God,” he gasped, as he spit up a crusty black substance with gray streaks, and then stared at the dead lung tissue staining the grass. Still coughing and breathing hard, Smith settled into a chair on his porch and clipped an oxygen tube to his nose.
After spending just 12 years underground, his lungs are so bad he faces what coal miners decades older and with decades more in mining have endured. His lung tissue is dying so fast, his respiratory therapist says, it just peels away.
“I’m terrified,” Smith said, as he remembered his father’s suffering when he was struggling with the same coal miner’s disease.
“I sure don’t want to go through what he went through. I seen a lot of guys that died of black lung and they all suffered like that.”

Kelly says he used to wrestle with his grandson before he was diagnosed with black lung disease. Fishing is one of the few activities he is still able to do.
Rich-Joseph Facun for NPR
hide caption
toggle caption
Rich-Joseph Facun for NPR
A multiyear investigation by NPR and the PBS program Frontline found that Smith and Kelly are part of a tragic and recently discovered outbreak of the advanced stage of black lung disease, known as complicated black lung or progressive massive fibrosis.
A federal monitoring program reported just 99 cases of advanced black lung disease nationwide from 2011-2016. But NPR identified more than 2,000 coal miners suffering from the disease in the same time frame, and in just five Appalachian states.
And now, an NPR/Frontline analysis of federal regulatory data — decades of information recorded by dust-collection monitors placed where coal miners work — has revealed a tragic failure to recognize and respond to clear signs of danger.
For decades, government regulators had evidence of excessive and toxic mine dust exposures, the kind that can cause PMF, as they were happening. They knew that miners like Kelly and Smith were likely to become sick and die. They were urged to take specific and direct action to stop it. But they didn’t.
“We failed,” said Celeste Monforton, a former mine safety regulator in the Clinton administration who reviewed the NPR/Frontline findings.

Kelly and his wife, Lisa, say grace before Sunday dinner.
Rich-Joseph Facun for NPR
hide caption
toggle caption
Rich-Joseph Facun for NPR
“Had we taken action at that time, I really believe that we would not be seeing the disease we’re seeing now,” said Monforton, now a workplace safety advocate who teaches at George Washington and Texas State universities.
“Having miners die at such young ages from exposures that happened 20 years ago … I mean this is such a gross and frank example of regulatory failure.”
It’s an “epidemic” and “clearly one of the worst industrial medicine disasters that’s ever been described,” said Scott Laney, an epidemiologist at the National Institute for Occupational Safety and Health.
“We’re counting thousands of cases,” he said. “Thousands and thousands and thousands of black lung cases. Thousands of cases of the most severe form of black lung. And we’re not done counting yet.”
“They’re essentially suffocating while alive”
This advanced stage of black lung leaves lungs crusty and useless, says Dr. Robert Cohen, a pulmonologist at the University of Illinois, Chicago who has spent decades studying black lung and PMF disease.
“You have a much harder time breathing so that you can’t exercise,” Cohen noted. “Then you can’t do some simple activities. Then you can barely breathe just sitting still. And then you require oxygen. And then even the oxygen isn’t enough. And so … they’re essentially suffocating while alive.”

“There’s a lot of memories here, some good, some bad,” says Smith, while reflecting on his years working at the now defunct Solid Energy mine in Pike County.
Rich-Joseph Facun for NPR
hide caption
toggle caption
Rich-Joseph Facun for NPR
The toxic mine dust that causes severe disease isn’t coal dust alone. It includes silica, which is generated when miners cut sandstone as they mine coal. Many coal seams in central Appalachia are embedded in sandstone that contains quartz. And when quartz is cut by mining machines, it creates fine and barbed particles of silica dust — fine enough to be easily inhaled and sharp enough to lodge in lungs forever.
In the past 30 years, the biggest coal seams were mined out in Appalachia, leaving thinner seams coursing through sandstone.
“All the good seams were gone because there were hardly no solid seams of coal left,” the 54-year-old Kelly remembered. “And there [was] more rock in the coal.”
The silica dust that resulted from cutting that rock was far more dangerous than coal dust alone.
Silica is “somewhere around 20 times more toxic and can cause disease much more rapidly,” said Laney.
The NPR/Frontline investigation found thousands of instances in which miners were exposed — not just to coal dust but to dangerous levels of toxic silica dust. The federal Mine Safety and Health Administration’s own data chronicle 21,000 instances of excessive exposure to silica since 1986.
At the same time, NPR identified black lung diagnoses involving miners in their 30s who also experienced rapid progression to the advanced stage of PMF. Smith says he was diagnosed with PMF at 39. NIOSH has confirmed this trend in its studies.
“We’ve got the bodies to prove it”
NPR/Frontline analyzed 30 years of data collected by federal regulators. They measure coal and silica dust where miners are working, and in 85 percent of the samples collected silica was at safe levels. But for that other 15 percent — which amounts to 21,000 dust samples — the data show that miners were exposed to excessive silica levels that violated federal health standards.
“That’s what causes disease, is the excessive exposure,” said Jim Weeks, an industrial hygienist and mine dust specialist at MSHA in the Obama administration and at the United Mine Workers union before that.
An NPR review of mine dust regulations also found that federal enforcement does not directly address silica dust. If regulators measure too much silica in mine air, they place coal mines on much tougher limits for coal dust. That’s supposed to lower the silica exposure because coal and silica dust are often mixed.
But our investigation found that this indirect approach to controlling silica dust didn’t always work. MSHA’s 30 years’ dust sampling data show dangerous levels of silica or quartz where miners were working close to 9,000 times, even after coal mines were required to meet reduced limits for coal mine dust.
“They didn’t pay sufficient attention,” Weeks concludes. “And …we’ve got the bodies to prove it. I mean these guys wouldn’t be dying if people had been paying attention to quartz. It’s that simple.”

A coal processing plant sits abandoned near Smith’s home in Pike County.
Rich-Joseph Facun for NPR
hide caption
toggle caption
Rich-Joseph Facun for NPR
We found another example of overexposure in MSHA’s data. Each time federal mine inspectors issued citations for too much silica, which they did only a fraction of the time, they included an estimate of how many miners were affected. A review of those data shows more than 9,000 workers were exposed to silica levels that the regulations considered dangerous.
This excessive exposure to silica almost certainly happens more often than the data suggest. That’s because the data show only what happens when regulators are checking. The inspectors don’t check most of the time miners are working. Dust sampling takes place during regular mine inspections, which are scheduled four times a year in underground mines and twice a year at surface operations.
And until recently, sampling did not take place every hour miners worked or while mines were at full production.
Another finding of the NPR/Frontline investigation: During some of the heaviest periods of exposure to silica, regulations allow miners to work without any monitoring for it at all.
A white rock dust
Smith drove us past a pair of adjacent coal mines near his home in Canada, Ky., where he and other miners cut nothing but rock for months.
He was reluctant to pull over at the Rockhouse Energy Mine, even though it is closed, because security guards were watching from a parking lot. So he slowly passed by, describing work shifts that lasted 16 hours a day, seven days a week, for months, while cutting through solid rock. They used drills and mining machines to dig from one coal seam to another underground.
“It wasn’t coal dust that you would see,” Smith said. “It was more of a white rock … dust.”
Smith and his coworkers were cutting what’s called a slope mine. It’s not really mining because there’s no coal involved. It’s all about cutting through mountainsides or blocks of rock to reach coal seams.
And because there’s no coal, it is considered development mining or construction. So sampling the air for toxic dust is not required, even though it is the most dangerous dust. Former MSHA officials told us some inspectors did it, but most did not.
Smith spent months cutting at least two slope mines in his career and believes that could explain his severe disease, even though he worked underground only 12 years.

An old photograph of Kelly taken when he was 19 captures him taking a break after working in the mines.
Rich-Joseph Facun for NPR
hide caption
toggle caption
Rich-Joseph Facun for NPR
“Very possible,” he said, as we passed the mine’s abandoned conveyor belts that stretch over the road. “Most of my mining career I run a continuous miner. I run a roof bolter also. And it’s very possible from all the hours we worked.”
Roof bolters operate a machine that pins roof supports into underground mines by drilling into solid rock. The machines have customized dust-control systems that suck away dust, but miners complain they get bursts of silica dust when they begin drilling and then later when they empty boxes that collect the dust that was sucked away during drilling.
The machine known as a continuous miner grinds up rock and coal. Dust is supposed to be controlled by massive ventilation fans that pump air through the mine, while heavy curtains channel that air to sweep away dust. Mining machines spray water as they cut, to tamp down dust.
NPR interviewed 34 coal miners, all diagnosed with PMF and with 12 to 40 years in mining in Pennsylvania, West Virginia, Virginia and Kentucky. Sometimes the dust controls worked, most told us, and sometimes they didn’t.
Federal law requires mining companies to offer dust masks or respirators to miners, but their use is not required. The law considers them a secondary and optional means of protection. Mines are required to provide air clear of dangerous dust, first and foremost.
Most of the sick and dying miners we interviewed who used dust masks said they often didn’t work.
“They would clog up with dust, sweat and spit,” said Edward Wayne Brown, who spent 21 years underground in Buchanan County, Va. “And then it feels like somebody just sitting there with their hand over your face.”
In fact, dozens of miners, including Smith, have filed product liability lawsuits against dust mask suppliers. Most cases are still pending but a few have resulted in multimillion-dollar verdicts for the miners.
“This is probably the oldest known occupational hazard,” said retired industrial hygienist Weeks, who has a collection of antique books to prove it — with references to mine dust hazards from Pliny the Elder in the first century and another dating to the 15th century.
“There’s nothing new about this,” Weeks added. “And you’d think by now we’d have figured out how to deal with it.”
Loading…
Don’t see the graphic above? Click here
Awareness of silica dust as a hazard in the United States goes back at least 100 years, with a series of studies and reports beginning in 1908. In the 1930s, hundreds of workers were sickened and killed by exposure to silica dust while tunneling through a mountain of solid rock in West Virginia.
In 1974, NIOSH first called for silica exposure limits twice as strict as those in place for coal miners and other workers. But it wasn’t until the 1990s that MSHA and others began to get serious about silica in coal mines.
NPR and Frontline obtained internal memos from the Clinton administration that showed alarm back then about clusters of advanced lung disease among coal miners as young as 40. MSHA sent out alerts to coal mining companies, warning about excessive exposure to silica dust and severe disease among miners. NIOSH again called for a silica exposure limit that would be twice as tough, plus separate regulation of silica, as did a Department of Labor advisory committee.
“We started a national campaign first to raise awareness,” recalled Davitt McAteer, the assistant secretary of labor for mine safety and health from 1994 to 2000.
“And it was that campaign that began to try to go after the silica requirements, raise the silica standard, and start on a separate path to control silica.”
McAteer proposed a major overhaul of the dust sampling system, which included other loopholes that permitted excessive exposures and inaccurate measurement of coal mine dust. But the effort encountered stiff opposition from the National Mining Association, the industry’s biggest lobbying group. The group sued over some elements of the plan and won.
“And then we ran out of time,” McAteer says. “And it’s something that’s unfortunate and put a lot of lives at risk.”
Mine dust loopholes
The regulation of silica dust wasn’t addressed during the administration of George W. Bush. During the Obama administration, mine safety advocate Joe Main was in charge of MSHA. Main was the longtime health and safety director at the mineworkers union and was on that Labor Department advisory committee that sought tougher regulation of silica back in 1996.
“It was very obvious that that whole scheme that had been in place, that has left so many people sick, had to be changed and had to be fixed,” Main said.
He was successful in closing major mine dust loopholes, and he deployed new technology — dust sampling devices that measured coal dust in real time and helped make sampling more immediate, honest and accurate.
Main also made the exposure limit for coal mine dust tougher. But not the exposure limit for silica. He didn’t include any specific action on silica in his plan.
“A high tide rises all boats, as the saying goes,” Main explained. “We were going to get a benefit out of reducing overall dust exposure by what we did. [That] would not only lower coal mine dust but all dust that was part of that, including silica.”
But as the NPR/Frontline data analysis shows, that formula failed thousands of times in the past. Lowering overall mine dust doesn’t necessarily reduce silica exposure to safe levels.

Smith worked mostly for Sidney Coal Co. during his 12 years as an underground miner. Sidney was owned by Massey Energy, a defunct coal giant with multiple mine disasters in its history and a CEO who went to federal prison for conspiracy to violate mine safety laws.
Rich-Joseph Facun for NPR
hide caption
toggle caption
Rich-Joseph Facun for NPR
Monforton wonders why MSHA missed or ignored that part of the dust sampling data.
“The fact that [NPR and Frontline] went back for 30 years and looked at that data, and that data was available to the agency to assess as well, why wasn’t that problem recognized and rectified?” Monforton asked.
Main and other former MSHA officials say they thought they were doing what they needed to do to control silica.
Another agency did act on silica during the Obama administration. The Occupational Safety and Health Administration concluded a 44-year review of silica exposure by enacting tougher regulation of silica dust.
So now, every industry in the country that cuts rock, every industry except mining, has separate regulation of silica and an exposure limit twice as tough — the limit first recommended by NIOSH in 1974.
Mining companies also knew they were cutting more quartz, creating more silica dust, and exposing miners to toxic dust. They were not only clearly warned by MSHA in the 1990s; they could see what was going on in their mines. Cutting rock slows mining machines and hurts production. And rock has to be removed from coal before it can be sold.
So NPR and Frontline wanted to know why mining companies didn’t act on their own to protect their workers.
“Sure they could have done that,” responded Bruce Watzman, the National Mining Association’s top lobbyist for more than 30 years. “But … I’m not going to speculate on why they did or didn’t do what they chose.”
“Our focus here is forward looking,” he said. “How do we prevent this in the future? I can’t answer for … what happened in the past.”
Watzman also asserted that the industry “is doing far better today than we did in the past, far better.”
That assessment is based on new data from MSHA following the new coal mine dust rules that began to take effect in 2014. Since then, mining companies have met exposure limits for coal and silica dust 99 percent of the time, the data show.
MSHA cited the same data in a written statement to NPR and Frontline.
“The dust rule … has greatly reduced miners’ exposure to respirable dust,” wrote MSHA spokeswoman Amy Louviere, who also noted a sharp drop in the past 10 years in the percentage of mine dust samples with excess silica. Her statement did not address the NPR/Frontline findings showing 30 years of excessive exposure to silica.
“MSHA continues to work diligently to protect coal miners’ health,” Louviere said.
But NIOSH epidemiologist Laney isn’t convinced the problem is solved.
“They’re sampled very infrequently so we don’t know what’s going on with these miners when they’re not being sampled,” Laney said. “Ninety-nine percent of the time we don’t have information on that.”
That’s also the conclusion of a recent review by the National Academies of Sciences, Engineering and Medicine. The new coal dust rules, the review committee said, “may not guarantee that exposures will be controlled adequately or that future disease rates will decline.”
It will also take 10 years or more to know whether the new dust rules result in fewer cases of disease. It takes that long for disease to develop.
“I said I suspect silica. I didn’t say it was”
MSHA declined multiple requests for interviews with top agency officials, including David Zatezalo, a former coal company executive and industry lobbyist who now heads the agency.
So we showed up at West Virginia University in September where Zatezalo was scheduled to make a rare public appearance.
“You hear the phrase in health circles of progressive massive fibrosis, these sorts of things,” Zatezalo told an audience of mining engineering students, agency employees and industry executives and lobbyists.
“To me, I believe those are all clearly silica problems,” Zatezalo continued. “Silica is something that has to be controlled.”
But immediately after his speech, when NPR and Frontline approached him, Zatezalo seemed suddenly uncertain about silica and PMF.
“I don’t think that the science of the causation is that well-defined,” Zatezalo said.
Asked about the direct link between silica and disease he described in his speech, Zatezalo became defensive.
“No, I said I suspect silica. I didn’t say it was. … I think until such time as you figure out what it is you don’t really know,” Zatezalo responded.
So far, under Zatezalo, MSHA has no plan to address a tougher limit for silica dust or separate regulation of silica in coal mines.
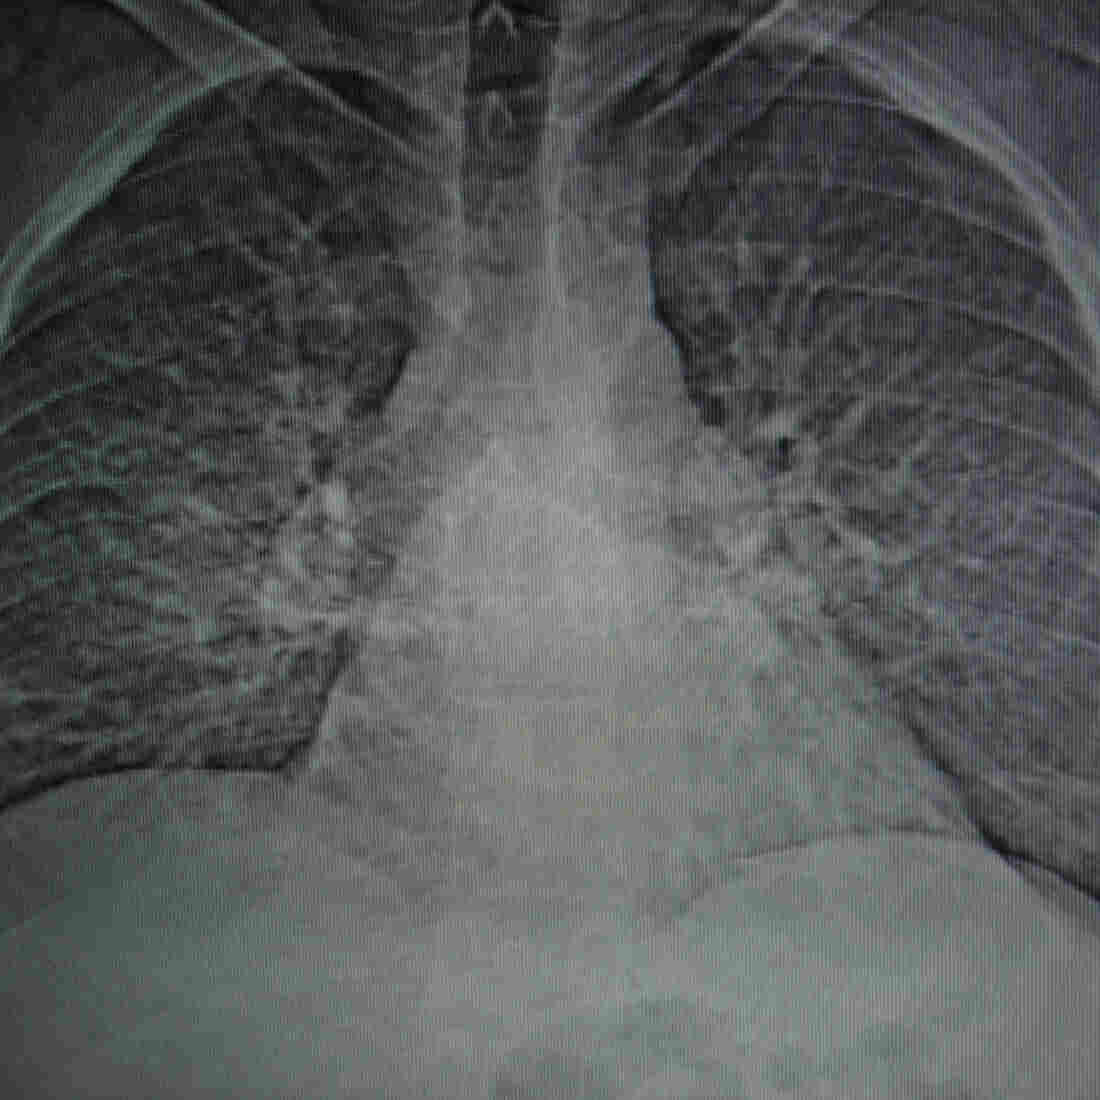
A CT scan shows the damage to Smith’s lungs caused by progressive massive fibrosis.
Rich-Joseph Facun for NPR
hide caption
toggle caption
Rich-Joseph Facun for NPR
In the meantime, the PMF epidemic continues. The biggest cluster of disease ever reported, according to NIOSH, continues to build at the Stone Mountain Health Services black lung clinics in Southwestern Virginia. The clinics continue to diagnose new cases at the rate of about a dozen a month.
“I’m not seeing any slowdown whatsoever,” says Ron Carson, who directed the Stone Mountain clinics for 28 years before retiring earlier this year.
“I think that America needs to know that these miners … have paid a price,” Carson added, his voice breaking. Carson cited the nation’s decades of dependence on coal for power and steel production.
“They paid a price so that we can have luxury and … so many have died. Thousands have died.”
“Every one of us is either crippled or dead”
Kelly has a long list of simple tasks he can no longer accomplish: walking up his driveway to the mailbox; climbing the few steps to his barn; riding horses; even just getting up to head to the bathroom. He has to stop and rest on the way, he says.
But what hurts the most are the things he can’t do with his grandson, Caden, especially playful wrestling on the floor.
“Now he has to wrestle a pillow while I call the match,” Kelly said, his voice halting and his eyes red. “It’s still fun, but …” and Kelly paused, his face tight and the tears flowing.
“I want to be that pillow.”

Incomplete projects are sprinkled around Kelly’s home. Kelly has a long list of simple tasks he can no longer accomplish; even just walking to the mailbox is difficult.
Rich-Joseph Facun for NPR
hide caption
toggle caption
Rich-Joseph Facun for NPR
Smith pulled up to another mine, which was also closed but had no guards in its weed-choked parking lot. This Solid Energy mine, along with the Rockhouse mine he drove by earlier, was operated by Massey Energy, now a defunct company with deadly mine disasters in its history and a CEO who went to prison for conspiracy to violate mine safety laws.
Smith got out and walked up to a rusted fence with a padlock. A ball cap shaded his face. Sunglasses hid his tears.
“It’s [been] eating at me for the last two years,” he said, “that I’m going to die over this. … Of all the things that could’ve killed me while I did work there, the rockfalls and all that stuff, I lived through all of that. And I find out years later I’m going to die over black lung. And it’s heartbreaking.”
Smith then mentioned his wife and two daughters and wondered what will happen to them when he’s gone. He wondered about the grandchildren he may never see. His voice breaking again, he talked about the excitement of being a young miner, about the hope and promise of good pay and good lives.
“We was all young and strong and stout and they took advantage of us. Every one of us is either crippled or dead. We was all young men,” he said, crying softly.

Smith has a plot picked out for himself in the family cemetery on his property, behind the gravestone of his parents.
Rich-Joseph Facun for NPR
hide caption
toggle caption
Rich-Joseph Facun for NPR
Back at his house in a narrow valley — a holler — in Canada, Ky., Smith pointed to a family cemetery on a knoll at the edge of the lawn he has so much difficulty mowing. It features a single gravestone with bright flowers and the names of his parents. Behind it, Smith told us, in the shade, is the burial plot he has picked out for himself. He’s 46 years old.
NPR’s Adelina Lancianese, Barbara Van Woerkom, Katie Lawrie and Cat Schuknecht; Benny Becker and Jeff Young of Ohio Valley ReSource; and Ellen Smith of Mine Safety and Health News contributed to this story.
VA Still Arbitrarily Cutting Caregivers From Program, Even As It Aims To Expand

Ret. Sgt. Christopher Kurtz and his wife Heather Kurtz pose for a portrait on the couch in their living room on Dec. 10, 2018.
Erica Brechtelsbauer for NPR
hide caption
toggle caption
Erica Brechtelsbauer for NPR
Chris Kurtz is trying to keep his sense of humor. Even after the VA told him last summer that he no longer needs a caregiver.
“Apparently my legs grew back, I dunno,” he says with a laugh, and sinks into his couch in Clarksville, Tenn. And then he mentions that he probably can’t get out of the couch without help from his wife.

Caretaker Ashlee Williams helps her husband, Former Staff Sgt. J.D. Williams, begin the process of putting on a prosethic leg.
Erica Brechtelsbauer for NPR
hide caption
toggle caption
Erica Brechtelsbauer for NPR
In December 2010, a bomb blast ended his Army deployment to Afghanistan. He lost both legs above the knee and half of his left hand. Heather, then his fiancée, joined him at Walter Reed Army Medical Center and the VA suggested she apply for their new caregiver program.
The program was set up to support family members of Iraq and Afghanistan veterans. They’re mostly wives and mothers who receive a VA stipend to provide home health care that would otherwise cost the VA millions of dollars.
When it started in 2011, vets signed up in huge numbers, quickly overwhelming the VA staff assigned to the program.
In recent years many VAs have drastically cut their rolls — often with little explanation to the caregivers.

Top, Ret. Sgt. Christopher Kurtz waits for his chair after arriving home. Bottom left, Kurtz wheels himself up to his front door as his wife and caretaker Heather Kurtz follows behind. Bottom right, Kurtz rests his hand, which is missing fingers from his injury.
Erica Brechtelsbauer for NPR
hide caption
toggle caption
Erica Brechtelsbauer for NPR
The cuts come at a time the program is supposed to be growing. Congress approved a major expansion of the program in May, though implementation could take years.
Congressional sources confirmed that the VA has missed its first deadline in October to implement new IT for the caregiver expansion — raising serious concerns of further delay. VA says the department will not deploy the new system until it is ready and has been tested thoroughly.
But VA also recently blew through a deadline to fix the IT for a new GI bill rule, and did so without initially telling Congress about the delay.

Jillyan Motter holds her younger brother Gabriel Kurtz.
Erica Brechtelsbauer for NPR
hide caption
toggle caption
Erica Brechtelsbauer for NPR
Chris and Heather Kurtz had been getting the highest level of support — Tier 3. That meant a stipend, health care for Heather and quarterly visits from a nurse. But earlier this year, Heather Kurtz was told her standing in the program was being evaluated. And without anyone from the VA even coming to see them, the Kurtzes got dropped in July.
Not reduced to a lower tier, but simply told that Chris no longer needs any help from Heather.
“He’s all better now, all better,” she said sarcastically as Chris laughed. “So he doesn’t need a caregiver for anything.”
“It was part of my identity. And then to have a letter tell me, ‘Well you’re no longer on the caregiver program,’ it hurt like a punch in the gut. Because I didn’t stop caregiving. I’ve always been a caregiver and I always will be,” she says.

The home of Ret. Sgt. Christopher Kurtz and Heather Kurtz on base at Fort Campbell.
Erica Brechtelsbauer for NPR
hide caption
toggle caption
Erica Brechtelsbauer for NPR
The Kurtzes are not alone. Just across the border near Bowling Green, Ky., Ashlee and J.D. Williams also got bad news, around Thanksgiving.
J.D., a former Army sniper, lost three limbs in a bomb attack in Kandahar. He’s fiercely independent, and he still finds ways to bow-hunt and target shoot. But he can’t do basic things like put on his prosthetic legs without help from Ashlee.
“It’s a 24/7 job,” she says. “If he wants to put his legs on he needs assistance. He wants a shower, he needs assistance. It’s not my choice. I worked full time before, at a job I enjoyed. [I had] to walk away from that.”
The Williams were demoted to Tier 1 of the program — but once their story got negative media attention, they were quickly restored to a higher tier. Still, Ashlee Williams says the way the decision was so easily changed makes her nervous.

Former Staff Sgt. J.D. Williams poses for a portrait with his wife and caretaker Ashlee Williams.
Erica Brechtelsbauer for NPR
hide caption
toggle caption
Erica Brechtelsbauer for NPR
“We’re in the clear right now — but for how long? It could be next month and they reassess us again,” she says.
An NPR report this year found that some VAs across the country have cut their rolls drastically. The VA says it’s part of standardizing the program and removing some vets who never should have qualified.
But a VA inspector general report in August found that about half the time, the VA wasn’t adequately monitoring the veteran’s health when it dropped them.
“So many caregivers are having issues,” says Williams, “and there’s no one to look at their case.”
That’s certainly true for the Tennessee Valley VA. From 510 caregivers on its rolls early last year, there are now only 104 — a drop of 80 percent.
It’s not only Tennessee. A VA spokesman said nationally the total number on the program has decreased slightly as facilities more accurately and consistently identify veterans who meet eligibility criteria for the program.

Caretaker Ashlee Williams helps her husband, Former Staff Sgt. J.D. Williams, put on one of his prosethic legs.
Erica Brechtelsbauer for NPR
hide caption
toggle caption
Erica Brechtelsbauer for NPR
But it doesn’t feel more accurate to Sherman Gillums — he’s a paralyzed former Marine who uses the VA in Washington, D.C. His wife is his caregiver.
“I was also told that in order to stay on the program, that I needed to have gotten treatment in the VA within the last year,” he says, “or else I’ll be removed from the program.”
Gillums says he had been to the VA for treatment. He thinks either the administrator who contacted him didn’t seem to have complete access to his health records, or it was something worse.
“You could take that as just informing me of the policy or it seems like a veiled threat — that’s just how I took it,” he says.
Gillums is also a senior official with one of the country’s largest veterans organizations, AMVETs. And he’s the vice chairman of the VA’s own caregiver advisory committee. He thinks there’s an effort to shrink the program.
“I characterize it this way — beginning a purge,” Gillums says.

Old wheelchairs and prosthetic legs sit in a corner of Former Staff Sgt. J.D. Williams’ home.
Erica Brechtelsbauer for NPR
hide caption
toggle caption
Erica Brechtelsbauer for NPR
He says getting the program fixed is crucial — because it’s about to grow five or six times bigger.
Congress passed a law in May, the VA Mission Act, which begins expanding the program to caregivers for veterans who served before 9/11, starting with vets from World War II, Korea and the Vietnam era.
VA Secretary Robert Wilkie told NPR last month that improvements in the program are underway.
“I think we are close to fixing that. What was the Mission Act has done [is] provided us with more resources to go out into the community and find those families that we have not been supporting, from the Vietnam era in particular,” Wilkie said.
Families like Paula and Chris Minger in Temecula, Calif. Chris suffered an abdominal wound in 1973, and complications led the VA to rate him 100 percent disabled. Paula has been taking care of him — without any VA stipend — for over 30 years. He’s in and out of the hospital, and now he’s often bedridden at home.











Former Staff Sgt. J.D. Williams practices shooting with his bow in his backyard on Dec. 11, 2018. Williams uses his love of hunting not only as therapy for himself but for other disabled combat veterans.
Erica Brechtelsbauer for NPR
hide caption
toggle caption
Erica Brechtelsbauer for NPR
“He’s probably just the most amazing guy I’ve ever known in my life. His mind is so good. He’s an avid reader. He does everything he can to make himself better,” she says.
But now he’s 68 and she’s 67, and she’d love some help, so the caregiver expansion was great news.
“I’m thrilled by it — I can’t wait,” Minger says.
She’ll have to wait, though. The timeline isn’t clear for when the expansion will start.
Bipartisan sponsors in Congress said they wanted to make sure to get the program right before rolling it out — particularly an update to the IT system. Congressional sources said it could be one to three years before Vietnam vets get in – but that hasn’t been communicated to caregivers like Paula Minger, who thought she might be able to apply this spring.
“I’m speechless,” she said upon hearing the one to three year estimate. “Think how many will die before then.”
Kentucky Attorney General Vows To Protect The Affordable Care Act

NPR’s Ailsa Chang talks with Kentucky Attorney General Andy Beshear about the court ruling out of Texas last Friday that struck down the Affordable Care Act.