Freedom Of Movement Rule May Be The Cause Of High-Scoring NBA Games

David Greene talks to Tim Reynolds, who writes about basketball for The Associated Press, about why NBA scores are repeatedly climbing into the triple digits.
David Greene talks to Tim Reynolds, who writes about basketball for The Associated Press, about why NBA scores are repeatedly climbing into the triple digits.

Affordable Care Act navigator Nini Hadwen (right) helped Jorge Hernandez (left) and Marta Aguirre find a plan on the health insurance exchange in Miami in 2013. Today, with fewer navigators, much of that counseling is done by phone instead of in person.
Joe Raedle/Getty Images
hide caption
toggle caption
Joe Raedle/Getty Images
Enrollment is down sharply on the federal health insurance marketplace this fall, and the consumer assistance groups that help with sign-ups think they know why.
They don’t have the staff to help as many customers as before because the Trump administration slashed funding. The federal government is spending $10 million this year on navigators who help individuals enroll in coverage. The government spent $36 million in 2017 and $63 million in 2016.
“We don’t have the people to provide the enrollment assistance nor to do the outreach and marketing to let people know what’s happening,” says Jodi Ray at the University of South Florida. She’s overseen Florida’s largest navigator program since 2014.
Ray’s program received $1.2 million in federal funding this year, down from $5 million a year ago. Florida leads the nation in enrollment in the Affordable Care Act marketplace plans.
With less money, Ray can afford to pay only 59 navigators across the state this year, down from 152 a year ago. With fewer navigators, much of the group’s counseling is done by phone instead of in person. That complicates the job, she says, because it is much easier to talk with customers in person, while looking at dozens of health plans with different costs and benefits.
Open enrollment in the Obamacare plans began Nov. 1 and will run until Dec. 15 for the 39 states covered by the federal exchange, HealthCare.gov. The other exchanges — run by states — typically extend sign-ups until the end of December or into January.
All these health plans sold under the Affordable Care Act are for people who don’t get coverage via their workplace or the government.
Nationwide, navigator groups are scrambling to make up for the loss of federal funding to ensure they can help people make sense of their health insurance options.
Nationally, nearly 800 counties served by the federal marketplace will not have any federally funded navigators this fall — up from 127 counties in 2016, according to the Kaiser Family Foundation.
Federal officials say they are not providing funds for navigators in Iowa, Montana or New Hampshire because no organizations applied in those states.
Nearly 12 million people across the country — including nearly 9 million on the federal exchange — enrolled in Obamacare plans for 2018.
In the first 17 days of open enrollment, 1.9 million people chose a plan for the 2019 coverage year on HealthCare.gov, according to data released last week by the federal Centers for Medicare & Medicaid Services. That compares with nearly 2.3 million consumers who selected their coverage through the exchange during the first 18 days last year.
States with the largest enrollment drops include Pennsylvania (down 29 percent from last year), Missouri (down 27 percent) and Virginia (down 42 percent).
The annual enrollment tally is being closely followed, in part because 2019 marks the first year since the marketplace plans began in 2014 that Americans won’t be fined for failing to have health coverage.
But health insurance specialists think the lack of navigator funding could end up having a bigger impact on enrollment. Caroline Gómez-Tom, navigator program manager of Covering Wisconsin, says the end of the individual mandate penalty has been a “nonissue” among people seeking coverage.
“Some folks mention it, but at the end of the day they still walk away with health coverage,” she says. “The ability to have coverage at affordable prices outweighs the penalty being gone, because people still see health care insurance as important to have.”
Consumers generally have a greater choice of plans for 2019 as more companies enter the individual market and existing plans expand their areas of service. Plus, insurance premiums are dropping in some areas. And where they are rising, the rate of increase is among the lowest in several years.
Katrina McGivern, director of policy and public affairs for the Kansas Association for the Medically Underserved, says people in rural areas of the state will have the most difficulty getting help, as a result of funding cuts.
After five years of experience, she says, she is hopeful that people will be able to figure out how to sign up on their own.
Still, she adds, “we always see a need for people who need assistance to get through it.”
Kaiser Health News, a nonprofit news service, is an editorially independent program of the Kaiser Family Foundation, and not affiliated with Kaiser Permanente.

Reigning chess world champion Magnus Carlsen (right), from Norway, plays Italian-American challenger Fabiano Caruana in the first few minutes of round 12 of their World Chess Championship match on Monday in London.
Matt Dunham/AP
hide caption
toggle caption
Matt Dunham/AP
The World Chess Championship is heading toward a dramatic conclusion on Wednesday, which could give the U.S. its first champion since Bobby Fischer took the crown in 1972.
The players will embark on a series of fast-moving tiebreaks at the event in London, which will get faster and faster if they continue to draw.
Fabiano Caruana, the 26-year-old Italian-American prodigy who grew up in Brooklyn, is definitely the underdog. For 12 games so far, he has taken on the current world chess champion, Magnus Carlsen. And each game has ended in a draw.
“I’ve had mediocre years, I’ve had good years,” Caruana said in a recent interview with The New York Times. “This year has been the best by far.”
According to the organizer World Chess, it’s the first championship match where nobody has won a game through the first 12 games of regular play.
Carlsen, who is 27 and from Norway, has been on top of the game for much of his adult life. He’s held the world champion title since 2013.
But some observers think he may be losing his edge. “He’s a shadow of himself, of his best times,” chess grandmaster Judit Polgár tells NPR’s Here & Now.
Carlsen raised eyebrows at a crucial moment in Game 12, when he appeared to be in a stronger position, yet suddenly offered to leave the game as a draw.
“For whatever reason, he chose not to invest the energy and, instead, proposed a draw after 31 moves, which Caruana accepted,” according to a write-up from World Chess.
That decision was baffling to legendary chess grandmaster Garry Kasparov.
In light of this shocking draw offer from Magnus in a superior position with more time, I reconsider my evaluation of him being the favorite in rapids. Tiebreaks require tremendous nerves and he seems to be losing his.
— Garry Kasparov (@Kasparov63) November 26, 2018
“In light of this shocking draw offer from Magnus in a superior position with more time, I reconsider my evaluation of him being the favorite in rapids,” Kasparov wrote on Twitter. “Tiebreaks require tremendous nerves and he seems to be losing his.”
At the same time, World Chess pointed out that even though computer calculations say Carlsen was more likely to win when he offered the draw, “the position was complicated and it was clear that it would take a lot of maneuvering, and many hours, if Carlsen hoped to break through.”
“I wasn’t in a mood to find the punch,” Carlsen said after the game, according to FiveThirtyEight.
Polgár said Carlsen has previously been known for avoiding draws. She says the two players are very evenly matched. “I think he lost the appetite of winning, or it is not so much important for him to win again, somehow he cannot motivate himself so much as he could before,” she said.
These past 12 games have been played according to time regulations that mean each game can take hours. The players have 100 minutes each for the first 40 moves, with even more time added after that.
But on Wednesday, the pace of the game is going to speed up – a lot. The challenge of the tie-breaks is that play happens in smaller and smaller amounts of time.
The faster play is expected to work in Carlsen’s favor. He’s higher-ranked in styles of chess with tighter time regulations.
The first four tie-breaker games start with 25 minutes each on the clock, and 10 additional seconds after each move.
After those four games, if the scores are still tied, it moves to even faster rounds called “blitz games.”
First, the players play two games with five minutes each plus three seconds after each move. If they’re still tied, they’ll play another two games, and this could continue up to 10 games total.
And if it’s still even after the end of the blitz games, they’ll go to a round referred to as “Armageddon.”
The player who has white pieces gets five minutes on his clock, one more minute than the player who has black. But, should the game end in a draw, the player with black pieces is automatically the winner.
And unless the referee decides otherwise, according to the rules, the players will have just 10 minutes between each of these tie-break games.
Besides the coveted title of world champion, there’s a lot of money on the line. The players are duking it out for a prize fund of 1 million euros ($1.1 million). If it had been decided in regular games the winner would get 60 percent and the loser 40 percent — now, because it has gone to tie-break games, the winner will get 55 percent and the loser 45 percent.
It’s worth noting that it’s highly unlikely that the matches will actually get to the epic conclusion of a sudden death round.
In fact, according to calculations by FiveThirtyEight, there’s a 0.02 percent chance this World Chess Championship will end in Armageddon.
We’ll just have to watch to find out. Games kick off Wednesday at 10 a.m. ET.

Shereese Hickson was diagnosed with multiple sclerosis in 2012 and is unable to work. She supports herself and her son, Isaiah, on $770 a month.
Shane Wynn for KHN
hide caption
toggle caption
Shane Wynn for KHN
Shereese Hickson’s multiple sclerosis was flaring again. Spasms in her legs and other symptoms were getting worse.
She could still walk and take care of her son six years after doctors diagnosed the disease, which attacks the central nervous system. Earlier symptoms such as slurred speech and vision problems had resolved with treatment, but others lingered: She was tired and sometimes fell.
This summer, a doctor switched her to Ocrevus, a drug approved in 2017 that delayed progression of the disease in clinical trials better than an older medicine did.
Do you have a bill for us to look into?
If you have a billing experience that you’d like to share with NPR and Kaiser Health News, you can submit it here.
Genentech, a South San Francisco, Calif.-based subsidiary of Swiss pharmaceutical giant Roche, makes Ocrevus. The drug is one of several for multiple sclerosis that are delivered intravenously in a hospital or clinic. Such medicines have become increasingly expensive, priced in many cases at well over $80,000 a year. Hospitals delivering the drugs often make money by charging a premium on top of their cost or adding hefty fees for the infusion clinic.
Hickson received her first two Ocrevus infusions as an outpatient two weeks apart in July and August. And then the bill came.
Patient: Shereese Hickson, 39, single mother who worked as a health aide and trained as a medical coder, living in Girard, Ohio. Because her MS has left her too disabled to work, she is now on Medicare; she also has Medicaid for backup.
Total bill: $123,019 for two Ocrevus infusions taken as an outpatient. CareSource, Hickson’s Medicare managed care plan, paid a discounted $28,960. Hickson got a bill for about $3,620, the balance calculated as her share by the hospital after the insurance reimbursement.
Medical service: Two Ocrevus infusions, each requiring several hours at the hospital.
Service provider: Cleveland Clinic, a nonprofit, academic medical center based in Ohio. (Cleveland Clinic has provided financial support for NPR.)
What gives: Hickson researched Ocrevus online after her doctor prescribed the new medicine. “I’ve seen people’s testimonies about how great it is” on YouTube, she said. “But I don’t think they really go into what it’s like receiving the bill.”
That was particularly shocking because, covered by government insurance for her disability, she had never received a bill for MS medicine before.
“I have a 9-year-old son and my income is $770 a month,” said Hickson. “How am I supposed to support him and then you guys are asking me for $3,000?”
Even in a world of soaring drug prices, multiple sclerosis medicines stand out. Over two decades ending in 2013, costs for MS medicines rose at annual rates five to seven times higher than those for prescription drugs generally, found a study by researchers at Oregon Health & Science University.
“There was no competition on price that was occurring,” said Daniel Hartung, the OHSU and Oregon State University professor who led the study. “It appeared to be the opposite. As newer drugs were brought to market, it promoted increased escalation in drug prices.”
With Ocrevus, Genentech did come up with a price that was slightly less than for rival drugs, but only after MS medicines were already extremely expensive. The drug launched last year at an annual list price of $65,000, about 25 percent lower than that of other MS drugs, Hartung said. MS drugs cost about $10,000 per year in the 1990s and about $30,000 a decade ago.
“We set the price of Ocrevus to reduce price as a barrier to treatment,” said Genentech spokeswoman Amanda Fallon.
It was also probably a response to bad publicity about expensive MS drugs, Hartung said. “Now companies are very aware at least of the optics of releasing drugs at higher and higher prices,” he said.
Patients starting Ocrevus get two initial infusions of 300 milligrams each and then 600 milligrams twice a year. Cleveland Clinic charged $117,089 for Hickson’s first two doses of Ocrevus — more than three times what hospitals typically pay for the drug, said John Hennessy, chief business development officer at WellRithms, a firm that analyzes medical bills for self-insured employers.
As is typical of government programs such as Medicare, the $28,960 reimbursement ultimately collected by the Cleveland Clinic was far less — but still substantial.
“We kind of got ourselves in a pickle here,” he said. “We’re more excited about the discount than we are about the actual price.”
Hickson’s nearly $3,620 bill represented the portion that Medicare patients often are expected to pay themselves.
Last year, the Institute for Clinical and Economic Review, an independent nonprofit that evaluates medical treatments, completed a detailed study on MS medicines. It found that Ocrevus was one of three or four medicines that were most effective in reducing MS relapses and preventing MS from getting worse. But it also found that patient benefits from MS drugs “come at a high relative cost” to society.
At the same time, deciding which MS drug — there are about a dozen — would best suit patients is something of a shot in the dark: The science showing the comparative effectiveness of MS drugs is not as strong as it could be, researchers say.
“In general, there’s a real lack of head-to-head studies for many of these drugs,” said Hartung. The [Food and Drug Administration] has no required comparison standard for MS drugs, an agency spokeswoman said. Sometimes they’re rated against placebos. With everyone able to charge a high price, the companies have little incentive to see which works better and which worse.
Resolution: After Hickson questioned the charges over the phone, the billing office told her to apply to the hospital for financial assistance. Hickson had to print a form, provide proof of her disabled status, mail it and wait.
Hospital officials told her in October she qualified for assistance based on her income through a state program funded by hospital contributions and federal money. Cleveland Clinic wiped out the $3,620 balance.
“I’m grateful that they approved me for that, but not everybody’s situation is like that,” she said. She was worried enough about being billed again for her next Ocrevus infusion that she considered switching back to her old medicine. But her doctor wants her to give it more time to gauge its effects.
The takeaway: Always ask about charity care or financial assistance programs. Hospitals have different policies and wide discretion about how to apply them, but they often do not even tell patients such programs exist.
Because health care costs can be so high, you may be eligible even if you have a decent salary. Cleveland Clinic gives free care to everybody below a certain income, said spokeswoman Heather Phillips. But it wasn’t until Hickson called that the hospital agreed to erase the charge.
“I’ve seen people’s testimonies about how great it is” on YouTube, said Hickson about the drug Ocrevus. “But I don’t think they really go into what it’s like receiving the bill.”
Shane Wynn for KHN
hide caption
toggle caption
Shane Wynn for KHN
While there are multiple new drugs to treat serious chronic conditions, they have often not been tested against one another. Moreover, your doctor may have no idea about their prices. But he or she should.For newer drugs, all options may well be very expensive.
Keep in mind that drugs that must be infused often come with facility fees and infusion charges, which can leave patients with hefty copayments for outpatient treatment. Ask about oral medicines or those you can self-inject at home.
NPR produced and edited the interview with Kaiser Health News’ Elisabeth Rosenthal for broadcast. Marlene Harris-Taylor, from member station Ideastream in Cleveland, provided audio reporting.
Do you have an exorbitant or baffling medical bill that you’d like KHN and NPR to look into? You can tell us about it and submit a copy of the bill here.
KHN is a nonprofit news service covering health issues. It is an editorially independent program of the Kaiser Family Foundation that isn’t affiliated with Kaiser Permanente.

Dr. Kimberly Remski was told by a potential employer that she couldn’t provide abortions during her free time, something she felt called to do. “I realized it was something I really needed to do,” she says.
Kim Kovacik for NPR
hide caption
toggle caption
Kim Kovacik for NPR
Doctors who are opposed to abortions, don’t have to provide them. Since the 1970s, a series of federal rules have provided clinicians with “conscience protections” that help them keep their jobs if they don’t want to perform or assist with the procedure.
Religious hospitals are also protected. Catholic health care systems, for example, are protected if they choose not to provide abortions or sterilizations. Doctors who work for religious hospitals usually sign contracts that they’ll uphold religious values in their work.
But as the reach of Catholic-affiliated health care grows, these protections are starting to have consequences for doctors who do want to perform abortions — even as a side job.
Religious hospitals often prohibit their doctors from performing abortions — even if they perform those abortions at unaffiliated clinics, says Noel León, a lawyer with the National Women’s Law Center. She was hired about two years ago to help physicians who want to be abortion providers. They have little in the way of legal protection, she says.
“Institutions are using the institutional religious and moral beliefs to interfere with employees’ religious and moral beliefs,” León says.
This kind of legal argument, León says, may prevent doctors from providing care they feel called to offer. And since many clinics that provide abortions rely heavily on part-time staff, it may also prevent these clinics from finding the doctors they need to stay open.
Dr. Kimberly Remski sought help from León when she was job-hunting. She is a primary care physician but had always been interested in women’s health. When she first set foot in a clinic that provides abortions, she realized it was her passion.
“A lot of the things we spend our time doing in training are monotonous, or you’re getting swamped in work,” she says. “I just remember leaving the clinic feeling like I was doing something really important.”
She interviewed for a job as a primary-care doctor with IHA, one of the largest physician groups in Michigan in 2017. She says she was clear about her desire to work one day a week in an independent clinic that provides abortions.
Part-time work is common for outpatient physicians, and Remski says the doctors she interviewed with were receptive.
“I was very upfront. I told that them that was a special interest of mine. I wanted to be able to pursue it,” she says.
She signed a contract, and started preparing for her move. Then she got a call that the offer was off.
Noel León oversees a National Women’s Law Center program that provides legal support to doctors who want to perform abortions.
Mary Mathis for NPR
hide caption
toggle caption
Mary Mathis for NPR
Remski learned that her potential employer was actually owned by a larger Catholic hospital network called Trinity Health, and it requires physicians to “provide services in a manner consistent with the Ethical and Religious Directives for Catholic Health Care Services,” according to her contract.
And, she says, she was shocked to learn Trinity Health would also have had a say over how she spent her free time. IHA officials told her that she couldn’t work on the side as an abortion provider if she took the job, Remski says.
Trinity Health had merged with IHA in 2010, part of a wave of mergers that has led to a net increase in Catholic ownership of hospitals. According to a 2016 report from MergerWatch, an organization that tracks hospital consolidation, 14.5 percent of acute care hospitals are Catholic-owned or affiliated. That number grew by 22 percent between 2001 and 2016, while the overall number of acute care hospitals dropped by 6 percent.
And as Catholic-affiliated health care expands, says León, doctors increasingly encounter morality clauses that prohibit them from performing abortions.
León says she has worked with at least 30 physicians and nurse practitioners from 20 different states who faced problems similar to Remski’s when they disclosed to their employers, or potential employers, that they planned to provide abortions.
“They’re being told that, ‘We can’t provide the care we went into medicine to provide,’ ” León says. “We shouldn’t be putting providers in the position of caring for their patients or keeping their jobs.”
Representatives of IHA would not agree to a phone interview about Remski’s situation, but spokesperson Amy Middleton explained in an email that IHA “works hard with our physicians to enable them to pursue other positions.” But, she added, “outside work that interferes with a physician’s ability to serve patients or contradicts the organization’s practices could present a conflict of interest.”
IHA physicians follow Catholic health care guidelines, Middleton wrote, which requires that physicians “not promote or condone contraceptive practices.”
Dr. Barbara Golder, the editor of the Catholic Medical Association journal the Linacre Quarterly, says that language about morality is ubiquitous in contracts — and that it’s reasonable that religious institutions might not want to be associated with abortion providers.
“The person is seen primarily as Dr. X of Catholic hospital Y, and then it turns out that Dr. X of Catholic hospital Y is doing abortions on the weekends,” Golder says. “There’s sort of a cognitive dissonance about that. It’s in opposition to what Catholic health care is.”
According to Lance Leider, a Florida attorney who has reviewed hundreds of physician contracts, it is “exceedingly common” for contracts, not just at religiously-affiliated hospitals, to include language about the reasons an employer can fire a doctor, including but not limited to morality clauses.
“There’s always a laundry list of things the employer can terminate the contract for,” Leider says. “There’s usually a catch-all. Anything that calls into question the reputation of the practice.”
These clauses tend to be vague, León adds, which means employers can invoke them to prevent a wide range of activities, like political activity, controversial posts on social media, or, in religious hospitals, physicians spending time at clinics that provide abortions.
The restrictions may have ramifications not only for physicians, but for many clinics that provide abortions. Smaller clinics may be staffed almost entirely with part-time doctors, and when they can’t find enough, they’re sometimes left unable to meet the demand for services.
“We don’t have full-time doctors,” says Shelly Miller, the executive director of Scotsdale Women’s Center in Detroit, Mich., one of the clinics where Remski worked. “We really cannot afford to have a provider sit here all day and wait for patients to come in.”
Through her involvement with the National Abortion Federation, Miller often talks with other directors of small clinics that provide abortions, and sometimes other women’s health services. She says that many of her counterparts say they exclusively hire part-time physicians because they simply don’t need somebody full-time. If more physicians are prohibited from part-time abortion work, Miller worries it may put some smaller clinics out of business.
It’s hard to know exactly how many of these clinics primarily use part-time staff, according to Rachel Jones, who studies the demographics of U.S. abortion services at the Guttmacher Institute, a family planning research organization. Ninety-five percent of abortions take place in clinics as opposed to hospitals, Jones notes, which may be more likely to utilize a team of part-time staff.
León doesn’t have data to show how common it is for physicians to be threatened with termination for providing abortions. She guesses that doctors will either give up on providing abortions — or, like Remski did, look for a different job that allows them to. León spends much of her time speaking to groups of doctors about how to approach contract negotiation if they want to provide abortions.
Ultimately, Remski says she parted amicably from IHA, since “it felt like the wrong place for me.”
She ended up finding a job at an urgent-care clinic in Michigan, which allowed her to work part-time at three separate clinics that provide abortions. She has since moved to Chicago, where she also splits her time between providing abortions and primary care.
“I was providing a service that was needed and necessary,” Remski says. “I realized it was something I really needed to do.”
Mara Gordon is a family physician in Washington, D.C., and a health and media fellow at NPR and Georgetown University School of Medicine.

Four-year-old Violet (right) supervises as her mom Margaret Siebers pours a first-ever spoonful of honey for 1-year-old Frances to try. Siebers spent much of the end of her pregnancy with Frances confined to bed rest at her home in Milwaukee.
Sara Stathas for NPR
hide caption
toggle caption
Sara Stathas for NPR
The couch is dark brown corduroy with lumpy cushions. There are a few telltale smears of food, maybe yogurt or a banana, and some crumbs here and there. It’s a well-loved piece of furniture.
Margaret Siebers plops herself down in the center and reaches out to baby daughter Frances, who climbs onto her mother’s lap to breastfeed.
“This is where I spent several months,” says Siebers, with a shrug. Her 4-year-old, Violet, runs around nearby. “I could come downstairs and sit on the couch.”
Siebers was about halfway through her pregnancy with Frances, when health professionals guiding her care told Siebers she should be on bed rest. And the subsequent months, spent confined to a bed and couch in her small home in Milwaukee, turned her family’s life upside down.
Please Tell Us What You Think About Shots
Help us make Shots more relevant for you by completing an NPR research survey. Click here to start the questionnaire.
“My husband immediately quit his full time job,” Siebers says, “and he took care of me. I wouldn’t even get my own glasses of water. So I like to say that ‘I was on bed rest, and he was on house arrest,’ because he really couldn’t leave either.”
Siebers is just one of thousands of pregnant women who are put on bed rest by their doctors, nurses or midwives each year. The stated reason: Going to bed will help prevent a premature birth, or worse, a miscarriage. But there’s a major problem with this advice — there is no solid, scientific evidence that bed rest improves outcomes for pregnant women and their babies.
“The bottom line is that there’s never been any proven benefit of bed rest,” says Dr. Anne Drapkin Lyerly, an OB-GYN and professor of bioethics at the University of North Carolina at Chapel Hill. Lyerly and colleagues in 2013 did a review of the scientific research on bed rest as it relates to a variety of conditions, from early contractions to high blood pressure to carrying twins. They found no benefit.
In fact, women put on bed rest can suffer harm — physical, psychological and economic. “It doesn’t seem like a dangerous intervention in the same way we think about surgeries or medications,” Lyerly says. “But in fact it can be very dangerous.”
Siebers was about 22 weeks pregnant when she visited a radiologist for a routine ultrasound. It was a standard screening at that point in her pregnancy — one that checks the baby’s growth, proportions and organs to ensure the fetus is developing properly. The baby was doing great, the doctor told her. The fetal heartbeat was strong and the ultrasound looked perfect. But there was one point of concern: Siebers’ cervix was ‘shortened,’ which can be a sign that a woman is at risk of preterm labor.
“So that was really scary for us,” she says. “We’re at this appointment and the doctor’s looking at the baby and saying, ‘You’ve got a beautiful heart.’ And I’m thinking, ‘Oh great, they’ve got a beautiful heart and they might die.’ “
Siebers’ health care team at that point included a midwife, who was her primary caregiver, an obstetrician consulting on her case, and the doctors who performed the ultrasound. Because she’d had a miscarriage the year before, the team recommended she undergo a procedure called a cerclage to help keep her cervix closed. And they wanted her to stay in bed.
Margaret and Alex Siebers say they struggled make ends meet during the weeks Margaret was confined to bed rest during her pregnancy with Frances, who is now 1 year old. Alex had to quit his paid job for a time to take care of Margaret and their older daughter, Violet, who is now 4.
Sara Stathas for NPR
hide caption
toggle caption
Sara Stathas for NPR
Deb Studey, Siebers’ midwife, had cared for her during her previous pregnancy, which had ended in miscarriage at the end of the first trimester. Studey says she believes the bed rest may have helped Siebers carry this second child — Frances — to term.
“I know that being on bed rest was hard for Margaret. But I also knew, on the flip of that, having a 24-week baby in an ICU wasn’t going to be an easy outcome either. So, in my mind,” Studey says,”bed rest let her get to term.”
Studey is aware that the research doesn’t show bed rest to be beneficial. In fact, a 2013 study that specifically addressed the issue of a shortened cervix found that women who were prescribed activity restrictions during their pregnancy were actually more likely to give birth early.
“I think studies are always of interest,” Studey says. “I guess I pay attention just as equally to how things are working for women — and that doesn’t always fit a study. I think we’re all different.”
But Lyerly, the UNC bioethicist, tells NPR bed rest is not a benign intervention, and doctors and others who work with pregnant women need to think hard before prescribing it. And the American College of Obstetricians and Gynecologists cautions against it, for several medical reasons.
“One of the most dangerous things that can happen when a woman is on bed rest is having a blood clot,” Lyerly says. “You can have blood clots in your legs or in your pelvis. And if those clots travel to your lungs, it’s life threatening.”
She says women also risk losing muscle tone, becoming weak — just before they’re about to go through labor and then care for a child. And lying in bed can weaken bones, and reduce lung capacity. Some women become depressed.
“Women who are pregnant are not just ‘women who are pregnant,’ ” Lyerly says. “They are oftentimes mothers of other children. They are senators; CEOs; journalists; professors. They work in restaurants. They have jobs and they need their jobs.”
On a mid-November evening, the Siebers family is celebrating Frances’ first birthday. Margaret and her husband Alex have come home from work, where Alex had just injured his finger with a miter saw and was trying to clean and bandage the wound. Margaret made popcorn and peeled mandarins for the kids, as 4-year-old Violet twirled around the house in a whirlwind of red sparkles, and Frances climbed everything she saw.
It wasn’t a scene that lent itself to quiet time on the couch.
That’s why, when Margaret Siebers was told to stop moving, to go to bed, Alex Siebers, 33, quit his job to care for the family for several months.
“It felt kind of like ‘knocked out of society’ for a while,” Alex Siebers remembers, of the time his wife was confined to the couch. “Our daily routine, our lives and our connections with people — we lost touch. Because we were, you know, trapped in here just trying to make it.”
Sara Stathas for NPR
hide caption
toggle caption
Sara Stathas for NPR
“Her mobility was extremely limited,” he says, “and the fact that we live in this house where the bathroom’s upstairs, you know, wasn’t helpful.”
His wife would get up in the morning, use the bathroom and go downstairs to the brown corduroy couch. She’d write letters, watch Netflix, read books.
“I could go upstairs to use the bathroom,” Margaret recalls. “I tried not to go too often, just because I didn’t want to be up and down the steps too much. I would sit on the porch sometimes. But whenever I moved, I would try to stay where I landed for hours, if I could.”
She was able to continue working from bed, 24-hour a week, for her family’s company, Bagtags Inc., which makes lanyards and custom name tags for big events. But that was hardly enough to make ends meet.
The Siebers went on Medicaid. They also qualified for FoodShare, Wisconsin’s food stamp program, and WIC, the federal nutrition program for women, infants and children. Friends from church got organized to bring the family meals. And their landlord gave them a break on their rent.
Margaret received a small inheritance of $1,000, along with a tax return of about $800 that gave her some unexpected money.
“All of those things together helped us to get through,” she says, “but barely. If any of those things were missing, I don’t really know what we would have done. Maybe move in with relatives.”
And the family became isolated, says her husband.
“It felt kind of like ‘knocked out of society’ for a while,” Alex Siebers says. “Our daily routine, our lives and our connections with people — we lost touch. Because we were, you know, trapped in here just trying to make it.”
Kelly Jones, an economics professor at American University in Washington, D.C., and a senior research economist at the Institute for Women’s Policy Research, says prescribing bed rest diminishes the role of women in society.
“If you’re telling a woman to undertake an activity that you’re not certain is going to be benefiting her, and yet it’s keeping her away from her job, what you’re saying to her is ‘Your participation in the economy is not important,’ ” Jones says.
The practice can also more generally harm the standing of women in the workplace.
“We know that the gender wage gap really starts when a woman has her first child,” Jones says. She says that’s partly because women take on more household work and child care. “But there are also aspects of that, that come from false assumptions, or [from] discrimination in the workplace surrounding childbirth and motherhood.”
Sending women to bed reinforces the notion that they are fragile or weak, Jones says. And those long-term absences from the workplace can have lasting effects on a woman’s earning power.
Siebers’ consulting obstetrician, Sheldon Wasserman, says he’s seen women and men make huge sacrifices to ensure a successful pregnancy — including people who mortgage their homes to pay for fertility treatments and women who spend months in bed.
“The pursuit of having a child is one of the most fundamental desires,” he says.
Wasserman is chair of the Wisconsin section of ACOG. He knows what the research on bed rest says, and knows about ACOG’s recommendations against it.
“I’m kind of torn between the art and the science of medicine,” he says. “Have I seen over the years patients who were on bed rest who were able to have children when their previous obstetrical history is very poor? Yes, I have.”
It’s hard to quantify just how many pregnant women are ordered to bed each year by their doctors. A widely cited study from 1996 found that about 20 percent of women were prescribed bed rest at that time. A study two years later found that as many as 90 percent of maternal-fetal specialists order bed rest for some patients in high risk pregnancies.
The practice dates back to the time of Hippocrates, but became widespread in the late 1800s, when a British anatomist posited that if immobility heals broken bones, it likely could heal other ailments. The “rest cure” became standard medical care, according to Jacqueline Wolf, a professor of the history of medicine at Ohio University, who has written books about the history of pregnancy and childbirth.
Prescribing bed rest for pregnancy persisted in part, she says, because there was a notion that pregnant women were vulnerable to getting upset and hysterical.
“So, prenatal care brought out [among] obstetricians — virtually all of whom were men in the U.S. until the 1970s — a very intense and pervasive paternalism,” Wolf says. “If a woman had any sign of preterm labor or bleeding, she was to get complete rest. No visitors. No conversations. Darkened room — shades drawn. Even earplugs.”
The depth of research on the topic has changed since the 1970s. But bed rest is still widely prescribed. Today, women’s magazines, consumer advice web sites and even major medical centers include information about bed rest as a common practice that anyone may expect to face.
When NPR asked listeners if they’ve been on bed rest in the last year, more than 200 women responded in just four days.
Some said they’d spent just a few days in bed, or were told simply to ‘lighten up’ on their physical activity. Others, like Margaret Siebers, were given strict orders to stay in bed.
Siebers says she was aware that the research showed little benefit to her staying in bed.
“You better believe I spent a lot of that time lying on my back reading articles about the effectiveness of it,” she says. “So that was that was something that came up a lot.”
She asked her doctors if she could travel to her family’s cabin, and lay on the couch there, just for a change of scenery. She questioned exactly how much she could do. Could she cook? Walk her daughter one block to the park? The caregivers didn’t always agree. But in general it came down to this: The baby is OK, so don’t change a thing.
That rationale is particularly troublesome to Anne Drapkin Lyerly with UNC, because it can induce unearned guilt in the mother if something goes wrong with her pregnancy.
“When bed rest is prescribed, the implication is that it is useful and that the immobilization is what is going to present prevent whatever dreaded outcome — whether that’s preterm birth or miscarriage or preeclampsia,” Lyerly says. “If it ends up that a baby is born prematurely, or a woman develops preeclampsia, she is going to worry that she didn’t adhere to the recommendation well enough and will blame herself.”
Lyerly says she prescribed strict bed rest to one of her patients early in her career, and the pregnancy ended in miscarriage several hours after the woman took a shower.
“There was no amount of argument I could do to make her think it wasn’t her fault,” Lyerly recalls. “Because, after all, we had prescribed bed rest and she had gotten up.”
When Siebers’ pregnancy reached 37 weeks, a time when doctors believe it’s safe to give birth, the stitch that doctors had taken to hold her cervix closed was removed. She was allowed to get up and return to normal activity.
It was then a full three weeks before she went into labor, and gave birth to Frances.
“So maybe it worked really well, or maybe it wasn’t necessary,” Siebers says of her time spent on bed rest. But after all the family went through, she says, she doubts she’ll want to have another child.
Now, a year after Frances’ birth, both her parents have returned to full-time jobs.
Margaret Siebers sings Happy Birthday to Frances on the baby’s first birthday.
Sara Stathas for NPR
hide caption
toggle caption
Sara Stathas for NPR
The family gathers around a table, with little bowls of ice cream – one with a single candle for Frances. They sing an extra-long version of Happy Birthday, Margaret Siebers’ family tradition, and mom blows out the candle as Frances dips her fingers tentatively into her first ice cream.
Alex Siebers ponders the whole experience.
“It would be very disheartening to learn later on in life — after there had been much more study and research done on this — to find out that that hadn’t been necessary,” he says. “Because that was a real hardship for us. I can’t, obviously, attribute the outcome to the bed rest completely. But, you know, there she is. You know — there’s the baby.”
The Siebers family, now relaxed, on the living room couch that limited their world for several months when Margaret was on bed rest. Today both parents have returned to full-time paid work.
Sara Stathas for NPR
hide caption
toggle caption
Sara Stathas for NPR

Infections with Clostridium difficile can crop up after a round of antibiotics.
BSIP/UIG via Getty Images
hide caption
toggle caption
BSIP/UIG via Getty Images
Named from the Greek kloster, for spindle, a class of bacteria known as Clostridia abounds in nature.
Staining deep violet under the microscope, they appear as slender rods with a bulge at one end, like a tadpole or maple seed. They thrive in soil, marine sediments and humans. They live on our skin and in our intestines.
And sometimes, they can kill you.
Most strains are harmless, but tetanus, botulism and gangrene are caused by clostridial species. Vaccination, sanitation and improved medical care have made these infections less common, but one variety has been difficult to contain.
Clostridium difficile, or C. diff, can cause diarrhea and a life-threatening infection of the intestines. The bug was associated with nearly 30,000 deaths in 2011.
First seen as a problem mainly confined to hospitals and nursing homes, research suggests C. diff rates in the community are on the rise, and that traditional risk factors may no longer tell the whole story.
C. diff was discovered in 1935 by scientists in Denver in the intestinal flora of healthy infants. The bacterium was harmless to the infants but proved lethal when injected into rabbits, providing an early clue to its danger.
At the same time, scientists in the United Kingdom were pioneering the use of penicillin to treat bacterial infections. The drug’s efficacy was near miraculous, but some patients developed severe diarrhea as a side effect. As antibiotics became widely available in the 1950s, this adverse effect became more common.
Early researchers speculated that Staphylococcus aureus, a common pathogen, was the cause. The usual treatment for staph is the antibiotic vancomycin, and many patients improved. But the true cause was C. diff — it was a stroke of simple luck that vancomycin is effective against both.
In 1974, scientists in Cincinnati discovered a toxin in affected patients’ stool, and traced it to C. diff.
A surge of interest in C. diff followed, and investigators quickly determined risk factors for the disease. Antibiotic use was already known, but hospitalization emerged as another dominant factor — so much so that C. diff became known almost exclusively as a hospital-acquired infection.
Clostridial species can revert to hardy spores that resist disinfectants, which is why so many infections occurred in hospitals and nursing homes. Health care workers were unknowingly spreading the spores and inoculating patients.
Scientists also began to ask why antibiotics triggered the infection. The answer appeared to be simple ecology. In healthy intestines, the sheer diversity of bacteria meant that C. diff couldn’t establish a foothold for out-of-control growth. But once a round of antibiotics had purged the normal flora, C. diff could take over.
Improved infection control in hospitals began to cut infection rates, but a few studies suggested that the problem might be bigger than anyone realized.
In 1991, Australian scientists found that C. diff was responsible for 5.5 percent of outpatient diarrheal infections, and researchers in Boston published additional evidence of community-acquired C. diff in 1994. Subsequent work confirmed the existence of C. diff in the community but suggested that the prevalence was low.
Things changed in 2006, when a hospital in North Carolina reported that 35 percent of C. diff infections were occurring outside the hospital, and that only half could have involved antibiotic exposures. A Centers for Disease Control and Prevention investigation, using different methods, found that 20 percent of infections had no recent health care exposure and only half had antibiotic exposure.
Work published in 2011 found that 40 percent of all C. diff infections in southern Minnesota were community-associated. Even more concerning, the investigators noted a marked increase over time of community-associated C. diff.
The CDC estimated that nearly 350,000 C. diff infections occurred outside of hospitals in 2011, and found that 46 percent were fully community-acquired and 36 percent had no antibiotic exposure. And just last year, researchers in California found that 1 in 10 emergency room patients with diarrhea tested positive for C. diff, and that 40 percent had no risk factors at all.
Traditional risk factors — antibiotics and hospitalization — can no longer explain many infections. Scientists have long suspected that antibiotics trigger C. diff infections by disrupting the intestinal microbiome.
Could it be that other factors are having a similar effect? Is our microbiome growing more susceptible to these dangerous infections?
Dr. Alice Guh, a researcher with the CDC, thinks so. “There’s definitely something going on,” she says, “but we don’t fully understand what.”
Diet strongly influences the microbiome and could be an element, she says. A recent study found that trehalose, a common food additive, markedly enhances the virulence of C. diff, although Guh cautions that there have been difficulties replicating the findings.
Guh thinks some common medications could be involved, too. Popular drugs for heartburn that suppress acid in the stomach are associated with C. diff infections, and have been shown to disrupt the microbiome.
And in March a study in Nature evaluated the effects of a thousand non-antibiotic medications on friendly bacteria in the human colon and found that 25 percent had antimicrobial activity.
Rising rates of C. diff infection in the community are a major public health concern. But could they be a sign of an even larger problem—that our guts are becoming ever more fragile? Scientists have already uncovered links between changes in the microbiome and a slew of other human diseases.
Perhaps C. diff is just a canary in the mine.
Clayton Dalton is a resident physician at Massachusetts General Hospital in Boston.

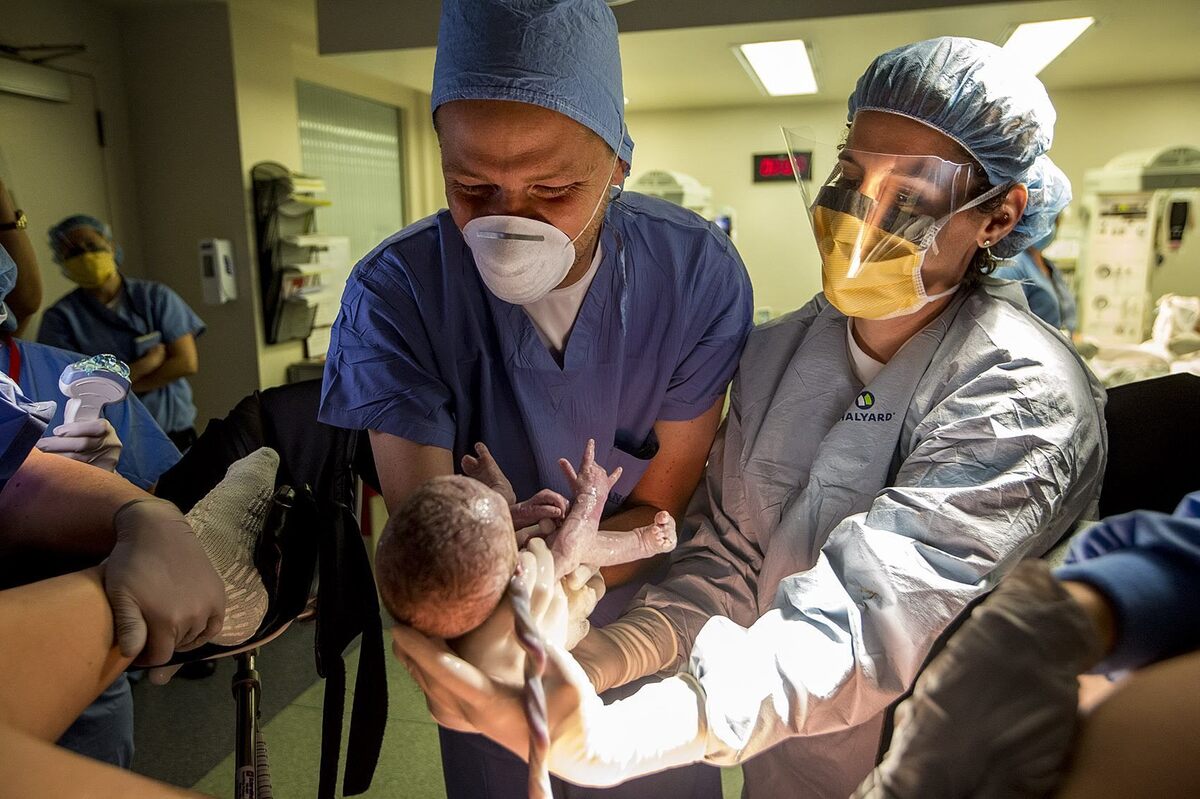
Dr. Ruth Levesque (right) hands Shaun McDougall his newborn son Brady at South Shore Hospital in Weymouth, Mass. The birth of the second twin, Bryce, was much trickier than Brady’s. Good communication between the health team and parents was crucial to safely avoiding a C-section, obstetricians say.
Jesse Costa/WBUR
hide caption
toggle caption
Jesse Costa/WBUR
The tiny hand and forearm slipped out too early. Babies are not delivered shoulder first. Dr. Terri Marino, an obstetrician in the Boston area who specializes in high-risk deliveries, tucked it back inside the boy’s mother.
“He was trying to shake my hand and I was like, ‘I’m not having this — put your hand back in there,’ ” Marino would say later, after all 5 pounds, 1 ounce of the baby lay wailing under a heating lamp.
This is the story of how that baby, Bryce McDougall, tested the best efforts of more than a dozen medical staffers at South Shore Hospital in Weymouth, Mass., one day last summer.
Please Tell Us What You Think About Shots
Help us make Shots more relevant for you by completing an NPR research survey. Click here to start the questionnaire.
Bryce’s birth also put to the test a new method of reducing cesarean sections that has been developed at Dr. Atul Gawande’s Ariadne Labs, a “joint center for health systems innovation” at Brigham and Women’s Hospital and the Harvard T.H. Chan School of Public Health in Boston.
The story starts before Bryce’s birth, on the last day of August at about 9:30 in the morning.
Melisa McDougall has just checked into South Shore, after a routine ultrasound. She’s in her 36th week, pregnant with twin boys. The doctors have warned Melisa that her placenta won’t hold out much longer. She’s propped up in bed, blond hair pulled into a neat bun, makeup still fresh, ordering a sandwich, when her regular obstetrician arrives.
“How are you?” asks Dr. Ruth Levesque, sweeping into the room and clapping her hands. “You’re going to have some babies today! Are you excited?”
The first of the twins — Brady — is head-down, ready for a normal vaginal delivery. But his brother, Bryce, is horizontal at the top of Melisa’s uterus.
That’s one reason Melisa is a candidate for a C-section. Babies do not come out sideways. And there’s another reason most doctors would never consider a vaginal delivery in Melisa’s case, Levesque says. Four years ago, she delivered the twins’ sister by cesarean.
“[Melisa] has a scar on her uterus,” Levesque explains, “so there’s a risk of uterine rupture — very rare, but there’s always a possibility.”
And that possibility may be greater for Melisa because she’s 37 years old and having twins. But the McDougalls hope to have vaginal deliveries for both boys.
“I just feel like it’s better for the kids — better for the babies,” Melisa says.
How the Team Birth Project came to be
Avoiding C-sections is also better for many moms. With cesareans, there’s a longer recovery period, a greater risk of infection and an association with injury and death. And most are not medically necessary, says Dr. Neel Shah, who directs the Delivery Decisions Initiative at Ariadne Labs.
Low-tech, but highly communicative, a whiteboard in the delivery room made sure all members of the birth team were clued in to procedures and preferences throughout labor.
Jesse Costa/WBUR
hide caption
toggle caption
Jesse Costa/WBUR
“We’re fairly confident that, when you look nationally, the plurality — if not the majority — of C-sections are probably avoidable,” says Shah.
Those avoidable C-sections are the focus of the Team Birth Project, designed by Shah with input from roughly 50 doctors, nurses, midwives, doulas, public health specialists and consumer advocates who focus on childbirth. South Shore Hospital is one of the pilot sites for the project.
In describing the collaboration, Shah begins with an acknowledgement: Childbirth is complicated. You’ve got two patients — the mother and the baby — and an ad hoc, often shifting team that at a minimum includes the mom, a nurse and a doctor.
“So you’ve got three people who have to come together and become a very high-performing team in a really short period of time, for one of the most important moments in a person’s life,” Shah says.
And this team has to perform at its best during an unpredictable event: labor.
Shah says doctors and nurses generally agree about three things: when a mom is in active labor; when a mom can definitely try for a vaginal delivery; and when she must have a C-section.
“And then there’s this huge gray zone,” Shah says. “And actually, everything about the Team Birth Project is about solving for the gray.”
To avoid unnecessary C-sections when what to do isn’t clear, this hospital, in conjunction with the Ariadne project, has changed the way labor and delivery is handled from start to finish.
First, women aren’t admitted until they are in active labor. Secondly, the mom’s preferences — such as whether she would like an epidural or not and whether she wants to have “skin-to-skin contact” with the baby immediately after birth — help guide the members of the labor team. The team members map the delivery plan — including Mom’s preferences and the medical team’s guidance — on a whiteboard, like the one in Melisa’s room.
For the births of Bryce and Brady McDougall, the white erasable planning board gets a lot of use.
Under “team,” Dr. Levesque and registered nurse Patty Newbitt write their names. Melisa and Shaun McDougall are also listed as equal partners. The names of other family members or nurses may be added and erased as labor progresses. Shah’s idea is that this team will “huddle” regularly throughout the labor to discuss the evolving birth plan.
The birth plan itself is divided into three separate elements on the board: maternal (the mom), fetal (the baby) and progress (in terms of how the labor is progressing). A mom with high blood pressure may need special attention — and that would be noted on the board — but she could still have a normal labor and vaginal delivery.
Good communication is key
Dr. Kim Dever, who chairs the OB-GYN department at South Shore, highlights a section of the whiteboard called “Next Assessment.”
That category is included on the board, Dever says, “because one of the things I often heard from patients is that they didn’t know what was going to happen next. Now they know.”
Asking the mom — and the couple — about their preferences for the delivery is crucial, too, Levesque says.
“It forces us to stop and to think about everything with the patient,” she explains.”It makes us verbalize our thought process, which I think is good.”
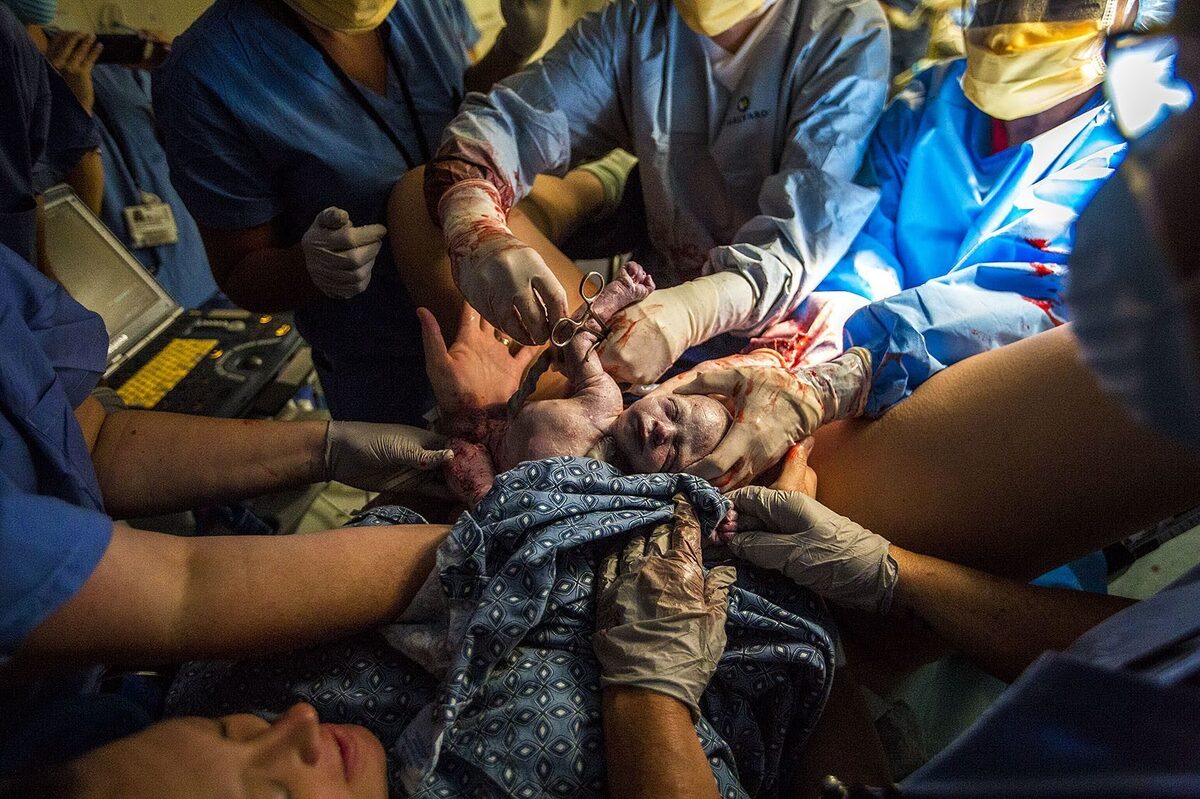
It took a large team — including parents — at South Shore Hospital to deliver this baby, Bryce McDougall.
Jesse Costa/WBUR
hide caption
toggle caption
Jesse Costa/WBUR
Shaun McDougall walks across the room to get a closer look at the whiteboard.
“Honestly, it seems like common sense,” he says. “I would always think the nurses would have something like this, but to have it out where mom and dad can see it — I think it’s pretty cool.”
With Melisa McDougall’s plan in place, everyone settles in, to wait. About four hours later, Melisa isn’t yet feeling contractions. Levesque breaks the water sac around Brady.
“Looks nice and clear,” Levesque reports. “Hey bud, come on and hang out with us,” she says to the baby, tickling his head.
“So, you’re going to keep leaking fluid until you leak babies,” the doctor explains to Melisa. “Whenever you start getting uncomfortable, we’ll get you an epidural at that point.”
Levesque moves to the board and adds updates: Melisa is 4 centimeters dilated; her waters broke at 13:26; the next assessment will be after she gets an epidural.
The medical team insisted ahead of time that Melisa agree to be numbed from the waist down if she wants to deliver Bryce — the second twin — vaginally. Melissa agreed. The obstetricians may need to rotate the baby in her uterus, find a foot and pull Bryce out, causing pain most women would not tolerate.
One of those doctors — Marino — peeks into the room and waves.
“Just came to say hi,” says Marino, who has more experience than most obstetricians in delivering babies positioned like Bryce. Along with Levesque, Marino has been seeing Melisa regularly in office visits.
Shaun McDougall asks the physicians if they’ll pose for a picture with his wife.
“Can we make funny faces?” asks Levesque.
“I want you to,” says Shaun. “You guys are like her favorite people on the planet.”
As the hours tick by, there’s a shift change, and registered nurse Barbara Fatemi joins the McDougall team. She checks Melisa’s pain level regularly to determine when she’s ready for the epidural.
Melisa says she isn’t feeling much but adds that she has a high tolerance for pain. Shaun tells Fatemi he sees the strain on his wife’s face. Fatemi acts on Shaun’s assessment and calls an anesthesiologist to prepare the epidural, something Shaun later says reinforces his feeling that they’re a team.
Levesque soon arrives for the promised “next assessment.” Melisa is now 10 centimeters dilated and ready to deliver — but she must hold on until nurses can get her into an operating room.
Levesque will still attempt to deliver both babies vaginally, she explains, but in the operating room, Melisa will be in the right place if Bryce doesn’t shift his position inside the uterus, and the doctor needs to do a last-minute cesarean.
“I’ll see you in a few minutes. No pushing without me, OK?” Levesque says over her shoulder as she heads to the operating room to prep.
“I’ll try,” Melisa says, weakly. In a minute, nurses are rolling her down the hall, following Levesque.
Almost five years ago, two women who were wheeled into this hospital’s operating rooms during childbirth died after undergoing C-sections. Though state investigators found no evidence of substandard care, Dever says the hospital scrutinized everything.
“When you have something like that happen, that expedites your efforts,” she says. “Exponentially.”
Now, Dever says, she sees an opportunity, through the Team Birth Project, to model changes that could help women far and wide.
“I would love women everywhere to be able to come in and have a safe birth and healthy baby,” she says. “That’s why I’m doing it.”
“They did not flinch”
Dever is about to see her pilot study of the Team Birth Project pushed to new limits by little Bryce McDougall. First, though, Melisa must deliver Bryce’s brother, Brady. Even his birth, the one that was expected to be easier, is more difficult than anticipated.
Bent nearly in half, her face beet red, Melisa strains for five pushes. She throws up, then gets back to laboring. And suddenly, there he is.
“Oh my goodness, Brady, oh Brady,” wails Shaun. He follows a nurse holding his son over to a warmer.
Marino takes Shaun’s place next to Levesque, who has reached inside Melisa to get the next twin. Levesque’s mission is to grab Bryce’s feet and guide him out. But everything feels like fingers, not toes.
“That’s a hand,” she murmurs. “That’s a hand, too.”
Marino rolls an ultrasound across Melisa’s belly, hoping the scan will show a foot. But Bryce’s feet are out of sight and out of reach.
Marino has had more experience than most obstetricians with transverse babies, and this procedure, known as a breech extraction; she asks to try. She reaches into Melisa’s uterus while Levesque moves to Melisa’s right side and uses her forearm to shift Bryce and push him down. Dever, the head of obstetrics, has come into the room and takes over the ultrasound. At least six doctors and nurses encircle Melisa, whose face is taut. Shaun frowns.
“Babe, you OK?” he asks.
Melisa nods. Bryce’s heart rate is steady. But there’s still no sign of a foot. One little hand slips out and Marino nudges it back in.
“Open the table,” says Marino, her voice strained.
It’s open and ready, her colleagues say, referring to the array of sterile surgical instruments that Marino may soon need, to begin a C-section.
For 36 seconds, this room with more than a dozen adults grows oddly quiet. Everyone is watching Marino twist her arm this way and that, determined to find Bryce’s feet. Levesque leans hard into Melisa’s belly. Shaun bites his lip. Then Marino yanks at something — and her gloved, bloodied hand emerges, clenching baby Bryce by his two teeny legs.
“Oh babe, here he comes, here he comes — Woo!” squeals Shaun.
Shaun is overcome with emotion again. Melisa manages an exhausted giggle. Baby Bryce keeps everyone waiting a few more seconds and then howls.
Levesque starts to stitch up a small tear for Melisa, and Marino comes around to congratulate the new mom.
“He was fighting you, huh?” Melisa says, and laughs.
Outside the operating room, Levesque and Marino look relieved and elated. Both agree that most doctors would have delivered Bryce by C-section. But at South Shore, the McDougalls found a hospital that has challenged itself to perform fewer C-sections and a doctor with experience in these unusual deliveries — one who knew and respected the parents’ preference.
“They specifically wanted to have a vaginal delivery of both babies,” Marino says — and that was on her mind during the difficult moments.
A nurse checks the breastfeeding progress with Melisa and Brady. Melisa says she’s grateful she was able to delivery both babies vaginally. “I did not want to have a natural birth and a C-section,” she says. “That would be a brutal recovery.”
Jesse Costa/WBUR
hide caption
toggle caption
Jesse Costa/WBUR
Bryce was fine, says Marino, so the deciding factor for her was that Shaun and Melisa did not panic.
“They did not flinch — they were like, ‘Keep going,’ ” Marino recalls. “Sometimes the patient will say ‘stop,’ and then you have to stop.”
The babies’ father says he came close to requesting that, in the very last minute before Bryce was born.
“That part with the arm — it was pretty aggressive,” Shaun says.
But in that moment, he adds, the feeling that he and Melisa were part of the team made a difference.
“It made us more comfortable,” Shaun says, and that comfort translated to trust. “We trusted the decisions they were making.”
Melisa says she’s grateful for the vaginal delivery.
“I did not want to have a natural birth and a C-section,” she says. “That would be a brutal recovery.”
Instead, 30 minutes after Marino pulled Bryce out of her, Melisa is nursing Brady and talking with family members via FaceTime.
Next assessment for The Team Birth Project
South Shore began using the Team Birth approach in April. Three other hospitals are also pilot sites: Saint Francis in Tulsa, Okla.; EvergreenHealth in Kirkland, Wash.; and Overlake in Redmond, Wash. The test period runs for two years. In the first four months at South Shore, the hospital’s primary, low-risk C-section rate dropped from 31 percent to 27 percent — about four fewer C-sections each month.
Experts who contributed to the development of the Team Birth Project are anxious to see whether other hospitals can lower their rates of C-section and keep them down.
“Once you get past the early adopters, how do you demonstrate the benefits for others that aren’t willing to change?” asks Gene Declercq, a professor of community health sciences at Boston University School of Public Health.
Declercq notes that a few insurers are beginning to force that question, refusing to include in their networks hospitals that have high C-section rates, or high rates of other unnecessary, if not harmful, care.
Declercq says the project’s focus on communication in the labor and delivery room makes sense because many physicians decide when to perform a cesarean based on clinical habit or the culture of their hospital.
“If you can impact that decision-making process, you can perhaps change the culture that might lead to unnecessary cesareans,” says Declercq.
The federal government has set a target rate for hospitals: No more than 23.9 percent of first-time, low-risk mothers should be delivering by C-section. The U.S. average in 2016 was 25.7 percent.
The target was put in place because research has shown that if a woman’s first delivery is a C-section, her subsequent deliveries are highly likely to be C-sections, too — raising her (and her baby’s) risk for complications and even death.
This story is part of NPR’s reporting partnership with WBUR and Kaiser Health News.
Scott Simon talks with NPR Sports Correspondent Tom Goldman about basketball, football, and golf.
SCOTT SIMON, HOST:
Brexit, shmexit (ph). It’s time for sports.
(SOUNDBITE OF MUSIC)
SIMON: The Warriors snap a losing streak, but there’s still a cold chill in the locker room and on the bench. And are Da Bears b-back (ph)? NPR’s Tom Goldman joins us now from – are you in your brother-in-law’s wood shop in Eugene, Ore., Tom? Is that true?
TOM GOLDMAN, BYLINE: I have turned off the skill saw for a few moments, Scott, where I’ve been working on a full-life sculpture of you.
SIMON: (Laughter).
GOLDMAN: Similar to the David, although clothed.
SIMON: Oh, oh. Well, thank you.
GOLDMAN: I’m here. I’m here for the holidays. And what better place to talk sports than a wood shop? So let’s do it.
SIMON: Right, efficient and all that stuff. Listen; that match play, or whatever you call it, last night between Tiger Woods and Phil Mickelson, which Phil Mickelson won in extra holes, or however you say it – two of them went home with $9 million between them. Is this a real sports event?
GOLDMAN: No. It’s pretty made up, Scott. The golf, apparently, wasn’t that good either. And I say apparently because I didn’t interrupt a second of my Black Friday to watch. And I say that as a golf lover and a golf watcher…
SIMON: Yeah.
GOLDMAN: …But not this one.
SIMON: And a great golfer, yeah.
GOLDMAN: Yeah, right. Well, thank you – hardly that. Let’s clarify the money, though. It was winner-take-all. So Phil made off with the 9 million.
SIMON: Oh.
GOLDMAN: He did donate part of it to charity, including a fund for children who lost a parent in last year’s Las Vegas mass shooting. This event was in Las Vegas, so some good came out of a silly event. Bah humbug. Wrong holiday, but bah humbug.
SIMON: Well, it’s coming up to the right holiday.
Golden State Warriors ended a losing streak last night. But prior to that, they’d lost four games in a row, unprecedented since the great Steve Kerr became head coach. He’s the smartest, most decent man in sports, if not the country at this point. But does mediating this undiplomatic dispute between Draymond Green and Kevin Durant need a Gandhi?
GOLDMAN: There’s an image for you. I think it might need a little something extra. You know, we’ve learned what, reportedly, was at the heart of the recent spat that led to Draymond Green’s suspension – the spat with Kevin Durant. It appears to be something more than just creative tension between two very creative basketball players.
Green reportedly made a comment in reference to Durant’s anticipated free agency at the end of the season and his possible departure from Golden State. According to Chris Haynes, respected NBA writer, Green said something like, we don’t need you. We won without you. Leave.
You know, Scott, that’s the kind of comment that can linger and poison the chemistry on a team. But if any coaching staff can deal with this, though, you have to think it’s the Warriors’, and especially Kerr, as you say, a very bright man who really understands the psychology of uniting a group of very talented athletes who have very huge egos.
SIMON: Yeah. He has more championship rings than he has fingers, if I’m not mistaken, between the six with the Chicago Bulls and the five in…
GOLDMAN: That’s right, yeah.
SIMON: Yeah, no, unless he’s grown extra fingers, and I wouldn’t put that past Steve Kerr.
Listen; have you noticed the Chicago Bears won their fifth consecutive game, albeit it was only against the Lions? But they are now 8-3 despite having a highly uninspiring quarterback who is out, and they had to go with a lackluster substitute. But, boy, that defense. (Growls) They even scored the winning point.
GOLDMAN: Yeah. (Imitating Scott Simon growling).
SIMON: And it’s against everything that football is supposed to be. What? Yes? They have me on the bench sometimes to inspire players. I just go. They come back after the play, and I go (growls).
GOLDMAN: You sound like…
SIMON: Yeah? Sorry.
GOLDMAN: You’re a Monster of the Midway. You are that, Scott.
You know, this defense is for real, ranked in the top 10 in the NFL and anchored by the very active and fearsome pass rusher Khalil Mack. Offensively, the Bears are not in the same class as the Saints or the Chiefs or the Rams – those three teams are kind of defining this new NFL surge in offensive play.
Still, the Bears, as you say, are 8-3. They’re leading the NFC North division. It’s looking – they’re looking to finish with a winning record for the first time since 2012, and perhaps the playoffs for the first time since 2010. Looks like Chicagoans won’t have to spend the winter just waiting for the Cubs to come back in the spring.
SIMON: Tom Goldman, thanks so much.
GOLDMAN: You’re welcome.
Copyright © 2018 NPR. All rights reserved. Visit our website terms of use and permissions pages at www.npr.org for further information.
NPR transcripts are created on a rush deadline by Verb8tm, Inc., an NPR contractor, and produced using a proprietary transcription process developed with NPR. This text may not be in its final form and may be updated or revised in the future. Accuracy and availability may vary. The authoritative record of NPR’s programming is the audio record.