Texas Sharpens Aim At Surprise Medical Bills In Bipartisan Proposal


The proposed legislation aims to reduce patients’ costs by beefing up a Texas Department of Insurance program that scrutinizes surprise balance bills greater than $500 from any emergency health care provider.
Kameleon007/Getty Images
hide caption
toggle caption
Kameleon007/Getty Images
A bipartisan group of Texas lawmakers announced plans this week to address surprise medical bills in a way they believe would ease the burden on patients in the state.
During a news conference Thursday, state Sen. Kelly Hancock, a Republican from suburban Fort Worth, announced he had filed a bill in the Texas Legislature aimed at preventing medical providers from, among other things, balance billing patients — charging patients the difference between what the health care provider and the medical insurer think a medical service or procedure is worth. State Rep. Trey Martinez Fischer, a Democrat from San Antonio, is filing a similar bill in the House.
If passed, the legislation would force medical providers and health insurers to mediate payment disputes before they send bills to patients. Hancock said the point of SB 1264 is to take “the burden off of patients.”
“[It] takes it off of their plates completely,” Hancock said.
He highlighted the case of Drew Calver, a public school teacher in Austin whose six-figure hospital bill after a heart attack was featured in a “Bill of the Month” investigation last summer by NPR, Kaiser Health News and KUT, NPR’s member station in Austin. Hancock noted Calver’s bill was reduced after the media attention but said it shouldn’t take such attention for a patient to get a reasonable bill.
Under this legislation, both sides of the payment dispute would settle their issues through an existing balance bill mediation program. The Texas Department of Insurance program has been successful in lowering medical bills across the state.
The legislation would beef up the program, which addresses surprise balance bills greater than $500 from all emergency providers — including free-standing emergency departments and all out-of-network providers working at a network facility.
“This is designed to apply in situations where patients don’t have any choice which facility they go to or which physician is involved in their care,” Hancock said.
Historically, the Insurance Department’s mediation program had many loopholes, and few consumers qualified for help. It was expanded in 2017, though, and more patients have been filing complaints.
For example, in 2014, the department was asked to mediate 686 medical bills. During the 2018 fiscal year, it received 4,445 bills.
Hancock said the program, so far, has saved Texas patients $30 million.
Still, consumer advocates argue, the system works only when patients know mediation is an option.
Stacey Pogue, a senior policy analyst with the Center for Public Policy Priorities, said patients don’t always know help is available, or they find the process intimidating.
“The instructions for how to do it are on your medical bill and your explanation of benefits — the most indecipherable documents you are going to get,” she told KUT earlier this year.
She and others have argued Texas should adopt a program similar to those in other states like New York, California and Florida, whose systems are more consumer-friendly.
Martinez Fischer said it’s time Texas officials stepped in to help patients who are caught in the middle of disputes between medical providers and health insurers. “It has been an industry issue for a few years, I grant you that — the health plans and the providers fighting over their business interests,” he said. “And I respect that. But 10 years later, it is a consumer issue.”
Among other things, Hancock’s bill would allow people with federally regulated, self-funded health plans to opt into the state’s mediation program. According to Hancock, those plans make up about 40 percent of Texas’ insurance market, but those consumers are currently not able to take part in the program.
Hancock said this should provide relief to consumers while federal lawmakers weigh their own efforts to address surprise medical bills.
“Texas will send a loud and clear signal to D.C. that similar consumer protections need to be passed at the federal level,” Hancock said. “Until then, Texas … [is] committed to doing something about it.”
U.S. Rep. Lloyd Doggett, a Democrat who represents Austin in Congress, said he is encouraged by Texas’ efforts but called federal protections “essential.”
“Only approval in Congress of legislation like my End Surprise Billing Act can both protect those who work for large employers with self-funded, federally regulated ERISA plans and assure that patients across America are not forced to pay the price for conflicts between insurers and health care providers,” Doggett said in a written statement.
This story is part of NPR’s reporting partnership with KUT and Kaiser Health News, an editorially independent news service of the Kaiser Family Foundation. You can follow Ashley Lopez on Twitter: @AshLopezRadio
Blair Braverman And Her 'Ugly Dogs' Prepare For Her First Iditarod


Rookie musher Blair Braverman and her dogs will compete in the Iditarod Trail Sled Dog Race, traveling more than 900 miles across Alaska from Anchorage to Nome and facing subzero temperatures and challenging trails.
Courtesy of Blair Braverman
hide caption
toggle caption
Courtesy of Blair Braverman
You know LeBron, Serena and Messi.
But do you know Pepe, Flame and Jenga?
They’re another kind of super athlete on a one-name basis with fans — sled dogs preparing for the Iditarod.
Blair Braverman, the team’s musher, will take her team out for the very first time when the race starts Saturday, braving some 938 miles of trail across Alaska, from Anchorage to Nome.
It’s a grueling race that took the last winner nine-and-a-half days to complete, with unpredictable conditions, mandatory rest breaks and the notorious “Happy River Steps,” three near-vertical drops early in the course, just one of the many possible pitfalls for mushers trying not to crash.
1. Pepé
We have many dogs who can lead the team, but our true Lead Dog — the pup who makes each run happen, who gets us through every storm — is Pepe. Pepe is smarter than all of us. She will run forever and keep running. She is basically everyone’s mother. pic.twitter.com/K6ckFTvv6l
— Blair Braverman (@BlairBraverman) January 2, 2019
But this rookie is ready. Braverman has shipped food out ahead of time on bush planes, studied the weather, repaired equipment and made and remade plans.
“How can you not overthink a 900-mile race?” she tells NPR’s Ari Shapiro. “There’s just so many different things that have to fall into place. It’s like chess in the snow.”
Braverman, a dogsledder, author and correspondent for Outside magazine, is one of 17 women racing in this year’s Iditarod, a record 32.7 percent of the field.
“Mushing is one of the only sports where men and women compete together at elite level,” she says. “We are taken seriously as athletes because there’s no chance for people to tell themselves we’re not on the same playing field.”
But she doesn’t consider herself just an athlete. She’s also a coach, a nutritionist, a parent, even a veterinary tech for her team. All of her dogs, 14 hand-picked racers from a group of 20 that she’s been training, have undergone physicals as extensive as the preparations for any professional athlete in the NBA or NFL, from EKGs to vaccinations.
“They were gone over with a fine-tooth comb by this great volunteer team of vets,” Braverman says. “And I’m happy to report that they all have top marks in all their health records, and they’re doing great.”
The dogs are a sharp but motley crew of strong personalities. Pepe is the steady, “mature” head of the pack. Flame is Braverman’s “shadow,” who has raced with her in every qualifier. Jenga is Flame’s half-sister who “doesn’t suffer fools.”
2. Flame (age 5)
Flame is my souldog. She is desperately codependent and we are both happiest when we are in physical contact at all times. She is also, to my occasional surprise, a fantastic sled dog. She finished every one of my qualifiers with me and never seems to tire. pic.twitter.com/JpWVcWxb94
— Blair Braverman (@BlairBraverman) January 2, 2019
And there are others, like Boudica, who loves gentle kisses, Colbert, a “big hunk” who is afraid of heights, and Grinch, who didn’t make the Iditarod team because he had some directional trouble. On a recent outing, he stopped in his tracks and refused to run after Braverman turned the sled around to head north instead of south.
“He has the biggest heart,” she says. “The most energy. And he’s incredibly stupid.”
It’s clear from the way she talks about them that Braverman loves her dogs. And that love affair led her to start writing and tweeting. She describes the racers like you’d write about old friends, sharing their quirks, thrills and setbacks with tens of thousands of followers. She calls her followers #UglyDogs, co-opting a phrase lobbed at her online.
“A Twitter troll actually told me, ‘Go back to your ugly dogs, Karen.'” (Her name isn’t Karen). “But I thought it was a beautiful sentence… Then some fans of the team said, ‘We should be the ugly dogs because you’ll always come back to us.’ So it took off.”
Braverman suspects her account has gained traction because dogsledding is a rural sport that takes place mostly out of sight – and her dogs give fans a way in. She spares no detail, from how to put booties on a dog that doesn’t like her feet touched, to her crew’s bowel movements.
Pleased to report that everyone’s poops have been extra great lately. pic.twitter.com/qE0rMDqCER
— Blair Braverman (@BlairBraverman) February 26, 2019
“People are getting to know these dogs as pets as friends, and they’re also seeing them as elite athletes,” she says. “It’s like rooting for your favorite sports team, but they all happen to be dogs.”
One of the biggest misconceptions that she’s trying to disperse? That the dogs are disposable. These are animals she’s been with for years, she says, and she knows each of them as individuals.
Jenga’s favorite head rest is her daughter, Hunter. pic.twitter.com/3c8E5SZdS4
— Blair Braverman (@BlairBraverman) January 4, 2019
“I think rather than telling people how much we love these dogs,” she says, “they can just feel how much we love these dogs, and how much we’re with them every step of the way.”
Braverman’s long days of preparation are winding down quickly. The Iditarod kicks in the Alaskan midmorning on Saturday, and she admits it’s terrifying to think about the race ahead.
But, she adds, “If I think about being out there with my dogs who are my best friends and my family, I just get so much strength from that.” The long days, the sleep-deprivation, the subzero temperatures – she’s tackling all of that with Pepe, Flame and the rest of her dogs. And that’s all the courage she needs.
The broadcast version of this story was produced by Dave Blanchard and edited by Matt Ozug.
Mark Sutcliffe: Do We Overstate Hard Work In The Narrative Of Success?

Part 4 of the TED Radio Hour episode Luck, Fortune, And Chance.
About Mark Sutcliffe’s TED Talk
Mark Sutcliffe says our luck—or privilege—is determined before we are even born. He encourages people to acknowledge the role of privilege in their lives and work to lessen the opportunity gap.
About Mark Sutcliffe
Mark Sutcliffe is an award-winning journalist, entrepreneur, and community activist.
He is the host of Ottawa Today, a daily four-hour talk show on 1310 NEWS and Rogers TV.
Additionally, Sutcliffe has founded several media properties, including the Ottawa Business Journal, the Kitchissippi Times community newspaper and iRun, Canada’s leading media brand for runners.
Sutcliffe has completed more than 20 marathons and is the author of four books: Why I Run, Canada’s Magnificent Marathon, Big Joe and the Return of Football, and Long Road to Boston.
Foes Of Trump's Restrictions On Family Planning Clinics See Law On Their Side


Abortion-rights activists gathered for a news conference in New York City Monday to protest the Trump administration’s proposed restrictions on family planning providers. The rule would force any medical provider receiving federal assistance to refuse to promote, refer for, perform or support abortion as a method of family planning.
Spencer Platt/Getty Images
hide caption
toggle caption
Spencer Platt/Getty Images
State attorneys general and women’s health advocates who are hoping to block in court new Trump administration rules for Title X, the federal family planning program, face one major obstacle: The Supreme Court upheld very similar rules in 1991.
Those rules were summarily canceled after a change in administrations. But the court is arguably more conservative than it was 28 years ago.
Still, those who oppose the Trump administration’s rules say that the ground has shifted. They expect to succeed in court this time, they say — pointing to protections enacted in the 2010 Affordable Care Act and changes made by Congress in the mid-1990s in bills that fund Title X.
“I don’t file a lawsuit unless I’m confident we will prevail,” Washington state Attorney General Bob Ferguson said at a news conference Monday, as he announced his plans to sue the Trump administration over the changes to the program. “We’ve filed 17 cases against this administration,” Ferguson said. “We have not lost a case yet.”
The new rules for Title X, posted Friday by the Department of Health and Human Services, are aimed primarily at evicting Planned Parenthood from the program — a longtime goal of abortion opponents. Currently no Title X money can be used for abortions. But conservative groups argue that since many Planned Parenthood affiliates receiving Title X support also provide abortions, the federal family planning money could be improperly commingled with funds used for the procedure.
Planned Parenthood affiliates serve about 40 percent of the program’s 4 million patients.
Specifically, Trump’s rules would forbid family planning providers in almost all cases from referring pregnant patients for abortion. It also would rescind previous regulations that require providers to give women with unintended pregnancies “nondirective” counseling about all their options. “Nondirective” counseling has meant that providers can neither encourage nor deter women from any specific action. Women’s health advocates, including Planned Parenthood, argue that changing that provision, as the Trump administration wants to, would hamper physicians and other providers from giving women unbiased advice, which they say is a violation of medical ethics.
The new regulations also would require any providers that also perform abortions to make those facilities physically and financially separate from their clinics that receive federal funds.
Planned Parenthood has not specifically announced that it will sue, but Dr. Leana Wen, the organization’s president, was clear last week in a call with reporters that “Planned Parenthood cannot participate in a program that would force our providers to compromise their ethics.”
And several other lawsuits are being lined up in anticipation of the rules’ formal publication in the Federal Register, expected next week.
The American Civil Liberties Union announced it will sue on behalf of the National Family Planning & Reproductive Health Association, which represents publicly funded family planning providers and administrators, as well as the Cedar River Clinics in Washington state. The Center for Reproductive Rights has said it will sue on behalf of family planning providers in Maine.
Several other state officials have said that they will sue, including officials in New York, Oregon and California.
Proponents of the administration’s move point to the 1991 Supreme Court case Rust v. Sullivan as proof that the rules are constitutional. In a 5-4 decision, the court said that very similar regulations issued by the Reagan administration in 1988 were an acceptable exercise of executive authority and did not violate the underlying law or the U.S. Constitution.
Although the rules were upheld, subsequent legal action meant they were in effect only for a month before again being blocked and then rescinded by President Bill Clinton in 1993.
Alliance Defending Freedom, a law firm that opposes abortion, released a statement regarding Trump’s new Title X rules that said, in part: “The Protect Life Rule, which the U.S. Supreme Court has upheld, will prevent organizations like the nation’s largest abortion business, Planned Parenthood, from funding their abortion activities through the Title X program.”
Opponents of the new rules, however, insist that the situation has changed in the years since that Supreme Court decision. For one thing, argued several members of Congress in a letter to HHS earlier this month, the department may have violated the federal Administrative Procedure Act that governs the crafting of regulations.
For example, the letter said, HHS “declined to deem the Title X rule economically significant — completely disregarding the considerable health-related costs the rule would impose — and failed to conduct a comprehensive regulatory impact analysis.”
And while the top court is more conservative than it was in 1991, “there are two new developments,” Washington Assistant Attorney General Jeff Sprung told reporters; “two statutes passed by Congress, that impose new requirements.”
One of those statutes involves language added to the spending bill that funded HHS in 1995 and was renewed in subsequent years. It restates the ban on using family planning funds for abortion, but also stipulates that “all pregnancy counseling be nondirective.”
In 2010, the Affordable Care Act added to that, with language that, among other things, bars HHS from issuing any regulation that “interferes with communications regarding a full range of treatment options between the patient and the provider” or that “restricts the ability of health care providers to provide full disclosure of all relevant information to patients making health care decisions.”
Leah Litman, an assistant professor of law at the University of California, Irvine, said the now more conservative Supreme Court might not necessarily accept those arguments, as well as others likely to be raised.
But there is no question, she said, that “the underlying scope of [the Title X program] has changed” since 1991.
Julie Rovner is chief Washington correspondent for Kaiser Health News, a nonprofit news service, which is an editorially independent program of the Kaiser Family Foundation and not affiliated with Kaiser Permanente.
NBA Proposes Lowering Draft Age To 18, 'USA Today' Reports

NPR’s David Greene talks to USA Today NBA reporter Jeff Zillgitt about the NBA’s proposal to update draft eligibility rules and what it would mean for aspiring basketball players.
On The Road To The World Cup, U.S. Women Tie Japan 2-2


U.S. forward Megan Rapinoe takes the ball as Japan’s Hina Sugita stays close on the first day of the SheBelieves Cup in Chester, Penn., on Wednesday night.
Elsa/Getty Images
hide caption
toggle caption
Elsa/Getty Images
With just a little more than three months to go until the Women’s World Cup in France, the U.S. squad is looking for proof it has all the right ingredients to affirm its ranking as number one in the world. But as the team left the pitch Wednesday night after a 2-2 tie with Japan, they acknowledged there’s still some tinkering to do – and that if they’re to defend their World Cup title, they can’t afford to make many mistakes.
It was the first day of the SheBelieves Cup, a tournament hosted by the U.S. in the run-up to the World Cup, which kicks off June 7. The game offered a rematch of the 2015 World Cup final, when the U.S. beat Japan 5-2. But both squads have changed significantly since then, and this four-team tournament provides a chance for each team’s coach to try new lineups — and see who will be making the trip to France.
But summer felt far away on this cold night outside Philadelphia, as a biting wind rolled off the Delaware River. Many players wore gloves, and spectators hesitated to take off their hats for the singing of the national anthem.
There were many young fans in the stands to catch the doubleheader — an earlier game saw England defeat Brazil 2-1 — and a high pitched chorus rose in excitement every time Megan Rapinoe, Tobin Heath, or Alex Morgan started on a breakaway run in the game’s early minutes.
Things started to go the Americans’ way in the 23rd minute, when Heath made a low cross that found Rapinoe, who slid it past Japan’s goalkeeper.
No. 17 on the field. No. 1 in our hearts.@TobinHeath does what she wants. pic.twitter.com/UJtQSviref
— U.S. Soccer WNT (@USWNT) February 28, 2019
The U.S. followed with numerous shots by Rapinoe and Morgan, but none found their way into the net.
In the 67th minute, Japan finally got its chance. Emi Nakajima bent a left-footer up and over U.S. goalkeeper Alyssa Naeher to tie the score.
We’re all tied up!
Nakajma gets Japan level after the USWNT fails to clear the danger. 1-1. #SheBelieves pic.twitter.com/9DUWrYLlVw
— FOX Soccer (@FOXSoccer) February 28, 2019
The momentum shifted to Japan, until the U.S. brought Christen Press off the bench midway through the second half. Almost immediately she found the ball and sent it to Morgan, who knocked it into the goal with her chest.
MORGAN GIVES THE U.S. THE LEAD!
That would be her first of 2019 and No. 99 for her USWNT career ?? #SheBelieves @alexmorgan13 pic.twitter.com/mhggcJk8ah
— FOX Soccer (@FOXSoccer) February 28, 2019
The U.S. seemed to have the game in the bag … until stoppage time, when Japan’s Yuka Momiki made a goal off the crossbar to tie it up in the 91st minute.
? Japan provide a late twist and score a last-minute equalizer against the USWNT! pic.twitter.com/xCoKzCm9fF
— FOX Soccer (@FOXSoccer) February 28, 2019
This was the U.S. team’s third match of 2019. The first was a 3-1 loss to France last month at Le Havre, the port city where the U.S. will play Sweden in the group stage of the World Cup. A few days later, the USWNT beat Spain, 1-0.
After the game, Rapinoe said the result showed that the team needs to work on closing games — and controlling them. “I think we still take too many risks when we don’t need to,” said the veteran forward. “And we should probably be more patient and wait for a great opportunity, instead of a half chance.”
She noted that it was the team’s third very different lineup as many matches. “We’re obviously still nailing that down.”
U.S. coach Jill Ellis said she was disappointed in the result, but not in the players or their performance.
“I thought there were some really good things” in both halves, she said. “I felt like we played as a team. We made two mistakes in the back that cost us. For sure we left things on the table. But in terms of our team play – what I asked the team to do defensively, the work ethic, the attacking — we got into their goal zone 34 times.”
She said she was going to take the positives from the game — and the team’s job is simply to keep getting better if it’s going to win another World Cup: “We have to play seven games to win this thing.”
The U.S. will face England on Saturday in Nashville, Tenn.
Coming Out Of Left Field: Baseball Superstar Bryce Harper Has Yet To Choose New Team
NPR’s Mary Louise Kelly speaks with The Ringer’s Claire McNear about the ongoing indecision from baseball superstar Bryce Harper over which MLB team he will join.
Bill That Would Regulate Doctors' Care Of Babies Who Survive Abortions Fails In Senate
The Senate failed to advance a bill that would regulate doctors’ care of babies who survive abortions. NPR’s Mary Louise Kelly talks with Washington Post reporter Mike DeBonis about the vote.
MARY LOUISE KELLY, HOST:
Yesterday, the Senate took up a bill that would have made sure doctors provide care for any child that survives an abortion. Fifty-three senators supported the bill, including three Democrats. That is not the 60 votes needed to avoid a filibuster, so the bill fails to advance. But even so, this issue is not likely to go away any time soon. The president offered his take soon after the vote, saying Democrats, quote, “don’t mind executing babies.” Here to discuss the bill and the politics behind it is Mike DeBonis. He covers Congress for The Washington Post, and he joins us now. Hey, Mike.
MIKE DEBONIS: Hey, Mary Louise. Thanks for having me.
KELLY: So what would this bill have done?
DEBONIS: Well, what it would’ve done would be to write into federal law that doctors, any health care provider would have to provide the same care to a child born after an attempted abortion that they would provide to any child born at the same gestational age. That is at the same time both very specific about what it requires doctors to do, which is do something – do the same as you would for another child, and it’s also very vague. It doesn’t say any particular type of intervention.
KELLY: So this prompts the question – is it clear that this law is needed to protect newborn lives? The sponsor of the bill, Senator Ben Sasse, Republican, and other Republican supporters of the bill say, yes, this is needed. This is about preventing doctors from committing infanticide.
DEBONIS: Well, there is a very strong dispute over how frequently these sorts of situations arise. Ben Sasse and other supporters of the bill say there are many occasions at which, after abortions, there are these children born alive. On the other hand, people opposing this bill say that these circumstances are exceedingly rare. And when they do happen, that these are in circumstances where you either have the life or health of the mother at stake, or you have a fetus, a child who is not likely to survive outside the womb for any length of time. And basically, their argument is that you are perhaps impairing a doctor’s best judgment at how to handle cases like this and that there are already standards and certainly laws in place to prevent infanticide, which is the word that the supporters of this bill keep using.
KELLY: And just to be clear, statistically, for a baby to survive in this situation, it needs to be fairly late stage in the pregnancy. And abortions performed at the very latest stages of pregnancy represent a small fraction of abortions overall.
DEBONIS: That’s right. We are talking about these very few cases that happen in the very latest stages of pregnancy.
KELLY: Give me a sense of what is happening on the state level in Virginia and New York, for example, that has led to this being debated at the national level.
DEBONIS: Sure. In New York, you had a successful push in the legislature to remove existing restrictions to late-term abortions. In Virginia, you had a unsuccessful effort to do largely the same thing. But it’s the Virginia bill that was ultimately unsuccessful that really sort of spurred a lot of interest in this when you had the governor of Virginia, Ralph Northam – he made some comments that were interpreted by a lot of conservatives to be what they considered a de facto description of infanticide. And that drove a lot of interest in this.
KELLY: All right. We saw President Trump taking it up in the State of the Union address, for example.
DEBONIS: That’s right. He referred directly to Governor Northam in what he said.
KELLY: The fact that this came to a vote in the Senate at all – Senate Majority Leader Mitch McConnell is famous for not letting bills come to the floor that he doesn’t want to come to the floor. What can you tell us about why he allowed this one to do so?
DEBONIS: Well, I think it’s pretty simple that he sees a political moment here in an issue that is uniting Republicans and dividing Democrats. You did see an uproar among conservatives after Governor Northam made his comments, and you did see some divisions in the Democratic ranks. You had three Democrats, including Doug Jones, who will be up for re-election next year, voting for it. So in Mitch McConnell’s mind, that’s a no-brainer. If it keeps your people united and divides your opponents, you should go ahead and put it up for a vote.
KELLY: Thank you, Mike.
DEBONIS: Thank you.
KELLY: He covers Congress for The Washington Post.
Copyright © 2019 NPR. All rights reserved. Visit our website terms of use and permissions pages at www.npr.org for further information.
NPR transcripts are created on a rush deadline by Verb8tm, Inc., an NPR contractor, and produced using a proprietary transcription process developed with NPR. This text may not be in its final form and may be updated or revised in the future. Accuracy and availability may vary. The authoritative record of NPR’s programming is the audio record.
Leaders Of 7 Pharmaceutical Manufacturers Face Tough Questioning On Capitol Hill
The CEOs of seven U.S. drug makers testified before the Senate Finance Committee on their pricing practices.
ARI SHAPIRO, HOST:
The leaders of seven prescription drug manufacturers faced hours of grilling on Capitol Hill today. They defended their business practices and tried to deflect outrage over high drug prices onto other parts of the health care industry. They also agreed in principle to lower prices if the Trump administration finalizes a proposal to their liking. NPR’s Alison Kodjak reports on the Senate Finance Committee hearing.
ALISON KODJAK, BYLINE: Republicans and Democrats on the committee seemed pretty fed up with the pharmaceutical industry. Drug prices are rising, and consumers are paying more at the drugstore. Committee Chairman Chuck Grassley made it clear that when it comes to drug prices, he didn’t want the same excuses he’s heard before.
(SOUNDBITE OF ARCHIVED RECORDING)
CHUCK GRASSLEY: We’ve all seen the finger-pointing, but like most Americans, we all – I at least, and I think you’ll find most members of Congress, are sick and tired of the blame game.
KODJAK: Grassley was referring to drugmakers’ habit of blaming the high prices they initially set, known as list prices, on insurance companies and middlemen known as pharmacy benefit managers because they both demand discounts off those prices. But Grassley was relatively kind in comparison to Oregon Senator Ron Wyden, the committee’s ranking Democrat.
(SOUNDBITE OF ARCHIVED RECORDING)
RON WYDEN: I think you and others in the industry are stonewalling on the key issue, which is actually lowering list prices, and reducing those list prices are the easiest way for American consumers to pay less at the pharmacy counter.
KODJAK: Drug companies routinely say their list prices are meaningless because people with insurance rarely have to pay that price. But Wyden and Grassley weren’t buying it.
(SOUNDBITE OF ARCHIVED RECORDING)
GRASSLEY: For seniors on Part D who are paying coinsurance as a percentage of list price, then for that person, list price is very meaningful. For people who have high deductible plans and pay thousands of dollars towards the list price, then for those people, the list price is very meaningful.
KODJAK: Wyden said those list prices are forcing patients into dangerous choices.
(SOUNDBITE OF ARCHIVED RECORDING)
WYDEN: It’s morally repugnant when ailing patients are forced to choose between filling the next prescription or putting food on the table because they can’t afford both.
KODJAK: All of the executives said they support a Trump administration proposal to change how drug prices are set. The way things work today, the deals pharmacy benefit managers negotiate on behalf of insurance companies come in the form of secret rebates. The Trump proposal would require the companies instead to offer upfront discounts that consumers get when they buy their drugs at the pharmacy counter. All of the executives said their list prices would fall if the proposal were finalized and it applied to government and private insurance plans. Albert Bourla is the CEO of Pfizer.
(SOUNDBITE OF ARCHIVED RECORDING)
ALBERT BOURLA: It is very clear intention that we will not keep a single dollar from these rebates. We will try to move every single penny to the patients.
KODJAK: The companies opposed another Trump proposal – to base the price that Medicare pays for some drugs on the prices that are paid in other countries. They also opposed allowing Medicare to negotiate prices directly with drug companies, as Democrats in the House and Senate have proposed. Olivier Brandicourt, CEO of drugmaker Sanofi, summed up what several of the witnesses said.
(SOUNDBITE OF ARCHIVED RECORDING)
OLIVIER BRANDICOURT: The government should not directly control the price of medicines either through federal government price controls or worse, outsourcing price decision to other countries
KODJAK: Senators also grilled the CEOs on their compensation practices, their use of the patent system and how much they spend on advertising. As the hearing wound down, it was clear that lawmakers are looking for concrete ways to cut what the government and consumers pay for prescription drugs. Alison Kodjak, NPR News, Washington.
(SOUNDBITE OF SLIDE FIVE’S “KC DOPPLER”)
Copyright © 2019 NPR. All rights reserved. Visit our website terms of use and permissions pages at www.npr.org for further information.
NPR transcripts are created on a rush deadline by Verb8tm, Inc., an NPR contractor, and produced using a proprietary transcription process developed with NPR. This text may not be in its final form and may be updated or revised in the future. Accuracy and availability may vary. The authoritative record of NPR’s programming is the audio record.
Double-Booked Surgeons: Study Raises Safety Questions For High-Risk Patients

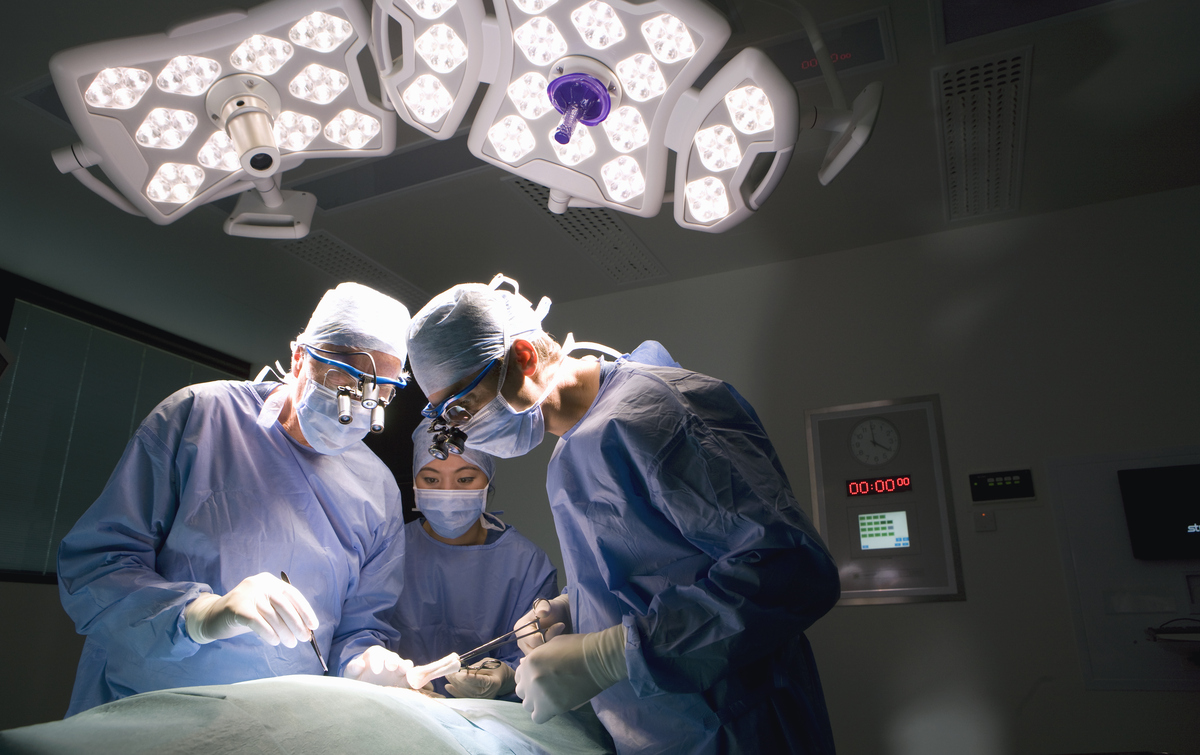
The common practice of double-booking a lead surgeon’s time and letting junior physicians supervise and complete some parts of a surgery is safe for most patients, a study of more than 60,000 operations finds. But there may be a small added risk for a subset of patients.
Ian Lishman/Getty Images
hide caption
toggle caption
Ian Lishman/Getty Images
Surgeons are known for their busy schedules — so busy that they don’t just book surgeries back to back. Sometimes they’ll double-book, so one operation overlaps the next. A lead surgeon will perform the key elements, then move to the next room — leaving other, often junior surgeons, to open the procedure and finish it up.
A large study published Tuesday in JAMA suggests that this practice of overlapping surgeries is safe for most patients, with those undergoing overlapping surgeries faring the same as those who are the sole object of their surgeon’s attention.
But the study also identified a subset of vulnerable patients who might be bad candidates; the practice of double-booking the lead surgeon’s time seemed to put these patients at significantly higher risk of post-op complications, such as infections, pneumonia, heart attack or death.
Researchers say Tuesday’s study by a multidisciplinary research team from several universities is the most comprehensive analysis of the practice to date, delving into the outcomes of more than 60,000 knee, hip, spine, brain or heart surgeries among patients ages 18 to 90 at eight medical centers. The study compared the outcomes of procedures done in isolation with those that were scheduled to overlap by an hour or more.
Dr. Anupam Jena, a physician and health economist on the faculty of Harvard Medical School and senior author of the study, says his research team found overlapping surgeries to be “generally safe.” Overlapping surgeries were not significantly associated with difference in rates of death or post-op complications.
These findings, says Jena, are in line with all but one of several such studies conducted since 2015, when an investigative team at the Boston Globe first turned searing attention on Harvard’s Massachusetts General Hospital. There, at one of the nation’s premier teaching hospitals, reporters highlighted a practice that at that point was little-studied and not widely discussed outside hospitals. In extreme cases, the surgeries were essentially concurrent, with the multi-tasking lead surgeon moving back and forth between ORs.
Within a year, the Senate Finance Committee jumped in with a report detailing lawmakers’ safety concerns about little-studied practice. And the American College of Surgeons updated its guidelines, adding that juggling “critical” parts of a surgery was “inappropriate.”
However, the less extreme practice of letting the beginning and end of surgeries overlap is still viewed by hospitals as an efficient means of deploying the skillful hands of their top surgeons. Mass General, which has continued the practice, is in the company of teaching hospitals nationwide. Overlapping surgeries in this way “offers greater and more timely access to certain surgical specialties,” Mass General says in an FAQ on the topic, “many of them high-demand, high-volume elective procedures.”
Jena says this is the first study to show that certain types of patients might particularly be at risk.
“This is the only [study] that breaks out and finds in certain high-risk groups, we might have worse outcomes”— namely, in older patients, those with pre-existing medical conditions, and those undergoing coronary artery bypass graft surgery, where blood flow is restored to the heart.
When the researchers homed in on these high-risk patients, they found slightly higher mortality rates among the patients who had undergone overlapping surgeries and were older or had underlying medical conditions — 5.8 percent compared with 4.7 percent for patients who had the lead surgeon’s full attention.
The scientists found a similar discrepancy in complication rates — 29.2 percent of high-risk patients experienced post-surgical complications when subject to overlapping surgery, compared to 27 percent of patients whose procedure was done in isolation. (The “complications” recorded in the study ranged from minor infections at the surgical site to heart attack or stroke.)
This discrepancy, says Jena, “could occur because a surgeon is separating their mental effort between two cases or [from] literally being [in] two places at once. Those kinds of problems would have a measurable effect on high-risk patients.”
The study also found that surgeries booked to overlap lasted a half-hour longer, on average, than those done in isolation.
Dr. Robert Harbaugh, former president of the American Association of Neurological Surgeons and current chair of the department of neurosurgery at Penn State’s Milton S. Hershey Medical Center, was not involved in the study, but says he was not surprised to see the findings show a “modest but real” risk posed to high-risk patients.
“In my practice, if I know someone is a very high-risk patient, you’re much less likely to (schedule) that patient for an overlapping surgery,” says Harbaugh. Surgical patients who have multiple underlying conditions, such as diabetes or hypertension, he says, require his full attention.
This study, he says, supports his sense that there is “a specific group of patients that probably has to be monitored more closely.”
However, Harbaugh says, overlapping surgeries are crucial “to make the operating room run more efficiently.” Surgeons are fully booked two or three months in advance in his department at Penn State, he says. Allowing four surgeries a day lets patients be treated that much sooner — as well as providing “the next generation of surgeons” much-needed training time.
The leading surgeon is always scrubbed-in for the “dangerous part of the surgery,” Harbaugh notes, and only leaves the patient with residents who are “competent to open or close a case.”
“If you’re finishing an operation and you tell your resident, ‘you can you go ahead and close the incision,’ they’re more than competent enough to do that,” he says. “Then you leave, go to another room where a [surgical] fellow has started a case. That’s an efficient use of time.” Harbaugh estimates 15 percent of the surgeries done by doctors in his department overlap.
Harbaugh also notes that his surgical department at Penn State requires surgeons to explain to patients when they sign the consent form that that they will be stepping out for parts of the surgery. But he doubts that policy of transparency is universal, he says.
Jena says there is “little information about what patients know” when it comes to the practice of overlapping surgeries. A 2017 study found few people had ever heard of the practice.
He says he and the study’s lead author, Dr. Eric Sun, an anesthesiologist and assistant professor at Stanford University, “both would agree that doctors should be telling patients about this practice.” Jena recommends patients ask, ahead of the operation, if their surgeon will be dividing their time.
If they don’t like the answer, Jena says, “At any point, the patient could say, “I don’t want care provided to me.”
Diana Zuckerman, a policy analyst and president of the National Center for Health Research, is doubtful many such conversations are likely to occur. “Most patients wouldn’t know to ask,” she says.
“The good news is, for an an individual patient, they shouldn’t worry,” Zuckerman says, pointing to the fact that the study found no significant increase in post-op problems or deaths overall.
However, she says, questions linger over whether patients should be informed about a surgeon’s other commitments, even if the risks of complications are low.
“I think it’s safe to say if patients were told, nobody would like it,” Zuckerman says. “Nobody wants to feel like the doctor is going in and out their surgery.